
What Does Finding Giardia in a Stool Sample Mean?
Giardia lamblia (also called Giardia intestinalis or Giardia duodenalis in different medical texts, all referring to the exact same organism) is a microscopic single-celled parasite, and it holds the distinction of being one of the most commonly identified intestinal parasites in stool testing anywhere in the world, in both developing regions and fully industrialized countries alike. If your stool sample came back positive for Giardia, the finding is neither rare nor mysterious — it's a well-understood, well-studied infection with a clear transmission story, a predictable set of symptoms, and, in the great majority of cases, a straightforward and highly effective course of treatment. What often generates the most confusion isn't the organism itself, but a handful of practical quirks in how it's detected: why testing sometimes needs to be repeated, why a single stool sample can miss it entirely, and why symptoms can occasionally linger even after the parasite itself is gone.
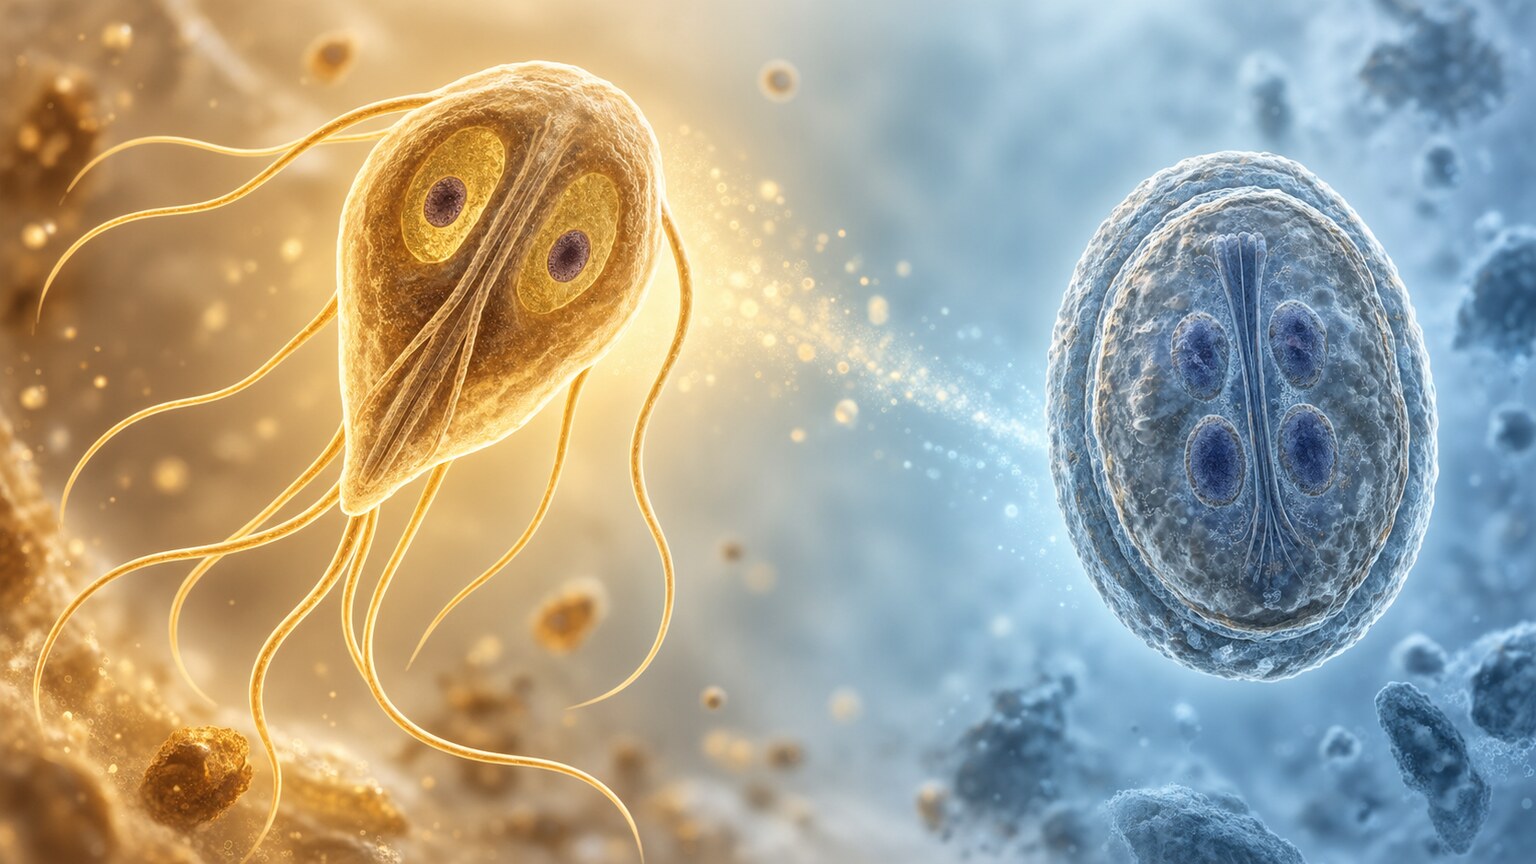
Figure 1. Giardia exists in two distinct forms — a fragile, active trophozoite that lives and feeds in the small intestine, and a tough, protective cyst that survives outside the body long enough to infect someone new.
The Two Faces of Giardia: Trophozoite and Cyst
Understanding Giardia starts with understanding that it exists in two genuinely distinct physical forms, each suited to a completely different part of its life cycle. The first form, called the trophozoite, is the parasite's active, feeding stage. Shaped somewhat like a teardrop or a kite, with two nuclei that give it a faintly cartoonish "face" appearance under a microscope and several whip-like flagella it uses to swim, the trophozoite lives attached to the lining of the small intestine, where it absorbs nutrients and reproduces. This form is fragile outside the body and cannot survive long once it leaves through a bowel movement, which is part of why it isn't the primary means by which the infection spreads from person to person.
The second form, the cyst, is what makes Giardia such a successful and widespread parasite. As trophozoites travel further down the intestine, some of them transform into a dormant, oval-shaped cyst surrounded by a tough protective wall. This cyst form is remarkably hardy — it can survive for weeks to months in cool, moist environments like lakes, streams, and even properly chlorinated swimming pools, since Giardia cysts are considerably more resistant to standard chlorine levels than most bacteria. When a cyst is eventually swallowed by a new host, stomach acid actually triggers it to release the active trophozoite form inside the small intestine, restarting the entire cycle. This two-form system, with a rugged, easily transmitted cyst and a fragile, disease-causing trophozoite, is a strategy shared by several other intestinal parasites, but Giardia is widely considered one of the most successful examples of it.
The infectious dose for Giardia is remarkably low compared with many other gastrointestinal pathogens — laboratory studies have found that swallowing as few as ten cysts can be enough to establish infection in a healthy person, whereas some bacterial causes of diarrheal illness require ingesting many thousands or even millions of organisms before infection takes hold. This low infectious threshold is part of why Giardia spreads so efficiently through casual contact and lightly contaminated water sources that might not raise any obvious suspicion, and it's a major reason public health guidance around this particular parasite emphasizes prevention measures capable of physically removing or destroying cysts entirely, rather than measures that simply reduce their overall numbers.
Once inside the small intestine, trophozoites attach to the intestinal lining using a specialized suction-cup-like structure on their underside called a ventral adhesive disc, allowing them to resist being physically swept away by the intestine's normal muscular contractions and the steady flow of digested material moving through it. This attachment mechanism, combined with the sheer numbers a single infection can produce through repeated cell division, is thought to be a major contributor to the malabsorption and bloating symptoms characteristic of the infection, since a dense carpet of attached trophozoites can measurably interfere with the intestine's normal ability to absorb nutrients, particularly fats, across the affected stretch of tissue.
How People Actually Get Infected

Figure 2. Drinking untreated water directly from lakes, streams, or rivers during outdoor recreation is one of the most classic and well-documented ways people become infected with Giardia.
Giardia spreads through what's known as the fecal-oral route, meaning infection requires swallowing cysts that originated in someone (or something) else's stool, however indirectly that transfer happens. Drinking untreated water from natural sources — lakes, rivers, streams, or even a seemingly clear mountain spring — is one of the most classic and best-documented routes, which is why the infection carries the nickname "beaver fever" in some regions, reflecting how commonly wild animals like beavers were historically implicated as a wildlife reservoir contaminating backcountry water sources. Hikers, campers, and other outdoor recreationalists are specifically counseled to filter or chemically treat any water sourced directly from the wilderness for exactly this reason, since natural-looking clarity says nothing about whether cysts are present.
Person-to-person transmission is at least as significant a route in practice, particularly in settings involving close contact and imperfect hand hygiene. Childcare centers and daycare facilities are well-recognized higher-risk environments, since diaper changes, close physical contact between young children, and developing hygiene habits combine to create ample opportunity for cysts to pass from one child to another, and outbreaks in these settings are common enough to be a recognized public health pattern. Swimming pools and water parks represent another surprisingly significant transmission route, precisely because Giardia cysts tolerate standard chlorination levels far better than most other waterborne pathogens; a single infected swimmer can introduce enough cysts to a pool to infect others, especially children, who tend to swallow more pool water during play than adults typically do.
International travel to regions with less reliable water treatment and sanitation infrastructure is another well-established risk factor, giving rise to the informal umbrella term "traveler's diarrhea," under which Giardia is one of several possible causes alongside various bacteria and viruses. Food can also serve as a transmission vehicle when it's been washed with contaminated water or handled by someone who is infected and didn't wash their hands adequately before food preparation. Less commonly, direct sexual contact involving oral-anal exposure can transmit the parasite as well, a route worth mentioning specifically because it's sometimes overlooked in discussions that focus primarily on water and food.
Pet ownership is a source of occasional confusion worth addressing directly, since dogs and cats can also carry Giardia and it's a commonly diagnosed finding in veterinary practice. Genetic studies of Giardia have identified several distinct strains, or "assemblages," and while some overlap exists, the strains most commonly infecting dogs and cats are generally different from the strains that most commonly infect humans, meaning transmission from a household pet to its owner, while not entirely impossible, is considerably less common than water-borne or person-to-person transmission between humans. Veterinarians and physicians alike generally don't recommend treating a household pet purely as a precaution against human infection unless the pet itself is showing symptoms or a specific strain match has been identified, since routine testing rarely changes the practical prevention advice already covered by good hand hygiene.
Curious what your own stool test results actually mean for your specific situation? Upload your results and get a complete, plain-language breakdown in under 15 minutes.
Analyze My ResultsWhat Symptoms Actually Look Like — and Why Some People Have None at All
The incubation period for Giardia — the time between swallowing a cyst and developing symptoms — typically runs one to three weeks, which is long enough that many people never connect their eventual symptoms back to a specific exposure like a hiking trip or a stay at a particular hotel. When symptoms do appear, the classic presentation includes persistent watery diarrhea (notably, one that's typically greasy-looking and unusually foul-smelling rather than bloody), prominent bloating and excess intestinal gas, cramping abdominal pain, nausea, and a gradual, unintentional loss of appetite that can lead to noticeable weight loss if the infection goes untreated for an extended period. Unlike several other causes of infectious diarrhea, Giardia infection classically does not cause fever or bloody stool, a distinction that can actually be clinically useful in narrowing down the likely cause of a patient's symptoms even before a stool test result comes back.
What surprises many people is how commonly Giardia infection produces no symptoms whatsoever. Studies looking specifically at this question have found that a substantial proportion of people who test positive for Giardia — in some populations, roughly a quarter to half of infected individuals — report no symptoms at all, and the parasite is only discovered incidentally, such as during testing performed for an entirely unrelated reason. This asymptomatic carrier state is part of why Giardia spreads so effectively through group settings: an infected person who feels completely well can still shed cysts capable of infecting others without any awareness that they're doing so.
Certain groups face a meaningfully higher risk of developing more severe or prolonged symptoms once infected. People with an underlying antibody deficiency, such as common variable immunodeficiency, are known to experience notably more severe and chronic Giardia infections than the general population, since antibodies play an outsized role in the body's ability to clear this particular parasite compared with how it handles many other infections. Similarly, people with chronic gastrointestinal conditions like inflammatory bowel disease sometimes experience a Giardia infection that's harder to distinguish clinically from a flare of their underlying condition, since the symptom overlap between the two can be considerable, which occasionally leads to a delayed diagnosis until targeted stool testing is specifically performed.
The severity and duration of untreated symptoms can also vary considerably based on how much of the small intestine ends up colonized and how robustly a given person's immune system responds. In most healthy adults, even an untreated infection eventually triggers enough of an immune response to at least partially control trophozoite numbers, sometimes leading to symptoms gradually easing over several weeks even without medication, though this natural partial control is inconsistent and unreliable enough that it isn't considered an acceptable substitute for actual treatment in someone experiencing ongoing symptoms.
Figure 3. Prominent bloating, gas, and cramping — often without fever or visible blood in the stool — form the classic symptom pattern that distinguishes Giardia from several other causes of infectious diarrhea.
Why a Single Negative Stool Test Doesn't Rule Out Giardia
One of the most clinically important quirks of Giardia is that it doesn't shed cysts into the stool continuously and predictably. Instead, shedding happens intermittently — a person genuinely infected with Giardia might have abundant cysts present in one stool sample and essentially none in a sample collected just a day or two later, purely due to the natural biological rhythm of the infection rather than any error in how the sample was collected or processed. This intermittent shedding pattern is precisely why standard clinical guidance for suspected Giardia infection, when using traditional microscopy-based testing, calls for collecting and examining three separate stool samples on three different days rather than relying on a single sample, since a single negative result carries a meaningfully higher chance of being a false negative compared with a series of three.
This is also where newer testing methods have made a genuine, practical difference. Stool antigen tests, which detect specific Giardia proteins directly rather than requiring a technologist to visually identify the parasite's structure under a microscope, tend to be considerably more sensitive per single sample than traditional ova and parasite microscopy, in part because they aren't as dependent on catching cysts during their unpredictable shedding windows. Molecular tests using PCR technology, which detect the parasite's genetic material directly, offer similarly strong single-sample sensitivity and are increasingly used, sometimes bundled into a multiplex panel that simultaneously checks for several different gastrointestinal pathogens from one sample. Because of these differences, a provider's choice of which specific test to order — traditional microscopy, antigen testing, or molecular testing — genuinely affects how many samples are needed and how much confidence to place in a single negative result.
It's worth understanding a bit more about why traditional microscopy specifically struggles with intermittent shedding in a way that antigen and molecular methods largely avoid. Microscopy fundamentally depends on a technologist directly visualizing an intact cyst or trophozoite in the small volume of stool actually examined under the microscope, meaning the organism must physically be present in that specific, tiny sample at that specific moment. Antigen and molecular tests, by contrast, detect either a protein or a fragment of genetic material that can remain present and detectable in the stool even when very few or no intact, visually identifiable organisms happen to be present in that same sample, giving these methods a meaningfully wider detection window per single collection. This technical distinction is also why a provider might specifically request an antigen or PCR-based test, rather than traditional microscopy, when there's a strong clinical suspicion of Giardia but an initial microscopy-based sample already came back negative.
Cost and availability differences between these testing methods are also worth knowing about, since they can influence which test ends up being ordered in a given clinical setting. Traditional ova and parasite microscopy remains widely available and comparatively inexpensive, and it carries the added advantage of simultaneously screening for a broad range of other parasites beyond just Giardia in the same single test, which antigen tests targeting a single organism cannot do. Antigen and molecular tests, while offering better single-sample sensitivity specifically for Giardia (and, in the case of multiplex panels, several other common targeted organisms), typically cost more and may not be available at every laboratory, meaning the choice of test sometimes comes down as much to practical availability and cost as it does to a pure sensitivity comparison between methods.
How Giardia Is Actually Treated

Figure 4. A short, well-tolerated course of an antiparasitic medication like metronidazole, tinidazole, or nitazoxanide successfully clears Giardia infection in the vast majority of treated patients.
The good news for anyone diagnosed with Giardia is that treatment is generally simple, short, and highly effective. Metronidazole, typically taken for five to seven days, has long been one of the most commonly prescribed options and carries a well-established track record, though it does require avoiding alcohol during treatment and for a short period afterward due to a genuinely unpleasant interaction, and some patients find its metallic taste side effect bothersome. Tinidazole works through a very similar mechanism but often clears the infection with just a single dose, making it an appealing option specifically for patients concerned about completing a multi-day course reliably. Nitazoxanide is another commonly used option, notable for being approved for use in children as young as one year old and available as a liquid suspension, which makes dosing considerably easier in pediatric patients who may struggle with swallowing pills.
Across these standard treatment options, cure rates in typical clinical use run quite high, generally in the range of 80 to 95 percent with a single completed course, meaning most patients are fully cleared of the infection without needing any additional treatment. For the smaller percentage of cases where symptoms persist or a follow-up test remains positive after an initial treatment course, providers generally move to a different medication class or occasionally combine two different antiparasitic drugs together, since certain Giardia strains have demonstrated reduced susceptibility to any single medication used alone. Treatment failure of this kind is uncommon but well-documented enough that it has an established management pathway rather than being a mysterious or unaddressed problem.
Asymptomatic Giardia carriers present a slightly more nuanced treatment question. Some clinical guidelines recommend treating essentially all confirmed cases regardless of symptoms, primarily to reduce further transmission to others, while other guidelines suggest treatment can reasonably be individualized, particularly in otherwise healthy adults with no symptoms and no particular risk of spreading the infection to vulnerable household members. This is a genuine area of clinical judgment rather than a single universally agreed-upon rule, and it's a reasonable topic to discuss directly with whoever ordered your test if your own result came back positive without any symptoms.
Pregnancy adds an additional layer of consideration to treatment decisions, since metronidazole and tinidazole are generally avoided, particularly during the first trimester, due to more limited safety data in pregnancy for this specific medication class. Paromomycin, a different antiparasitic medication with a better-established pregnancy safety profile, is frequently used as a preferred alternative in this situation, though it's generally considered somewhat less effective overall than the first-line options used outside of pregnancy. This is precisely the kind of situation where discussing treatment timing and medication choice directly with an obstetric provider, alongside whoever ordered the original stool test, becomes especially important, since the right choice can depend on how far along the pregnancy is and how significant the symptoms have become.
Drug resistance, while still relatively uncommon in Giardia compared with the resistance patterns seen in many bacterial infections, has been documented and is an area of ongoing research interest. Certain genetic markers within specific Giardia strains have been associated with reduced susceptibility to metronidazole specifically, which is part of why a treatment failure after a properly completed course sometimes prompts a provider to switch to a structurally different medication class entirely rather than simply repeating the same drug at a higher dose. Combination therapy, using two different antiparasitic medications together, has shown good results in the research literature for these harder-to-treat cases, though it's generally reserved for confirmed treatment failures rather than used as a routine first-line approach given the added cost and side-effect burden of taking two medications simultaneously.
Why Some Symptoms Linger Even After Successful Treatment
A genuinely important and sometimes frustrating aspect of Giardia infection is that certain symptoms can persist for weeks or, less commonly, months after the parasite itself has been successfully eliminated by treatment, confirmed by a negative follow-up stool test. The most well-documented of these lingering issues is a temporary, acquired lactose intolerance: the infection can damage the small intestine's lining enough to temporarily reduce production of lactase, the enzyme needed to digest the sugar in dairy products, leading to bloating, gas, and loose stools specifically after consuming dairy, even though the Giardia infection causing the original damage is already gone. This temporary intolerance typically resolves on its own over the following weeks to months as the intestinal lining fully heals, though some people choose to limit dairy intake during that recovery window to reduce symptoms in the meantime.
A smaller subset of patients experience a more prolonged pattern sometimes referred to as post-giardiasis irritable bowel syndrome, in which ongoing bloating, altered bowel habits, and abdominal discomfort continue for months after confirmed clearance of the infection, similar in concept to post-infectious IBS patterns seen after other gastrointestinal infections as well. The exact mechanism behind this lingering syndrome remains an area of active research, with current theories focused on lasting changes to gut motility, low-grade ongoing inflammation, and shifts in the normal gut microbial community following the initial infection. Importantly, having this kind of persistent symptom pattern doesn't indicate treatment failed or that the parasite is still present — a follow-up stool test confirming clearance, paired with this recognized clinical pattern, generally shifts the conversation toward symptom management rather than repeat antiparasitic treatment.
Chronic fatigue is another lingering complaint some patients report well after their gastrointestinal symptoms have fully resolved, and while this connection is less thoroughly studied than the lactose intolerance and post-infectious IBS patterns, some research has pointed toward changes in gut microbial diversity following Giardia infection as a possible contributing factor, since the gut microbiome plays a broader role in overall energy metabolism and immune regulation than its digestive functions alone would suggest. This remains an active area of investigation rather than a fully settled clinical picture, and providers generally approach persistent post-infection fatigue by first ruling out other, more common and more directly treatable causes before attributing it to lingering effects of a cleared Giardia infection specifically.

Figure 5. Whether a sample is examined by traditional microscopy, antigen testing, or molecular PCR methods meaningfully affects how confidently a single result can rule the infection in or out.
Giardia in Children, and Why Daycare Settings Deserve Special Attention

Figure 6. Daycare and childcare settings see disproportionately high rates of Giardia transmission, largely due to close physical contact between children and hygiene habits that are still developing.
Children, particularly those under five years old, experience Giardia infection at meaningfully higher rates than adults, and childcare centers are one of the single most consistently documented settings for outbreaks. Several factors combine to make this age group and setting especially vulnerable: young children have not yet developed reliable independent hand-hygiene habits, diaper changes create direct opportunities for cyst transfer between caregivers and children, and toddlers in particular explore their environment through frequent hand-to-mouth contact, all of which meaningfully increase the odds of swallowing cysts shed by another infected child. Public health data collected across various regions consistently shows daycare-associated Giardia outbreaks clustering in specific classrooms or age groups within a single facility, reflecting how closely these transmission opportunities track with the everyday routines of very young children rather than any facility-wide sanitation failure.
Diagnosing Giardia in young children carries a few practical nuances worth knowing. Because the classic symptoms — bloating, gas, and foul-smelling greasy stools — can be harder for a young child to describe and easier for a caregiver to attribute to a more common, benign cause like a temporary stomach bug or a new food sensitivity, infections can go unrecognized for longer in this age group than they typically would in an adult who can describe their own symptoms more precisely. Growth and weight patterns are watched somewhat more closely in children with a confirmed or suspected Giardia infection, since prolonged, untreated infection has a documented association with impaired nutrient absorption and, in more prolonged cases, measurable effects on a child's growth trajectory, an effect not typically seen to the same degree in otherwise healthy, well-nourished adults with the same infection.
Treatment considerations differ slightly for children as well. Nitazoxanide's approval for children as young as one year old, along with its availability as a liquid suspension, makes it a particularly practical first-choice option in pediatric cases, since younger children often cannot reliably swallow standard tablet formulations. Dosing for all antiparasitic medications used against Giardia is calculated based on the child's weight rather than a flat adult dose, and providers typically want to confirm resolution of symptoms directly with a caregiver at a follow-up visit given how much harder subtle, ongoing symptoms can be to self-report at this age.
Preventing Reinfection and Protecting Others in Your Household
Because Giardia spreads so readily through close contact, a confirmed diagnosis often prompts practical questions about protecting other household members, particularly if young children or anyone with a weakened immune system lives in the same home. Careful, frequent handwashing with soap and water, especially after using the bathroom and before preparing or eating food, remains the single most effective and universally recommended prevention measure, since alcohol-based hand sanitizers are notably less reliable against Giardia cysts compared with their effectiveness against many bacteria and viruses. Anyone caring for an infected young child, particularly during diaper changes, should pay especially close attention to hand hygiene immediately afterward.
Household surface cleaning is a reasonable additional precaution while a family member is actively symptomatic, particularly in shared bathrooms, though it doesn't need to become an excessive undertaking. Regular household cleaning products are generally effective against Giardia cysts on hard surfaces, and simply maintaining normal cleaning routines around toilets, sinks, and frequently touched surfaces during the treatment period is typically considered sufficient without needing specialized disinfectants.
For anyone planning outdoor recreation in areas with natural water sources, the standard prevention advice is straightforward: never drink directly from lakes, rivers, or streams without first filtering the water through a filter specifically rated to remove protozoal cysts (a standard general-purpose water filter isn't automatically sufficient), boiling it for at least one minute, or treating it with a chemical disinfectant specifically effective against Giardia, since boiling and appropriately rated filtration are generally considered more reliable against this particular parasite than chlorine-based tablets alone. Travelers heading to regions with less reliable water treatment infrastructure are generally advised to stick to bottled or otherwise verified safe water, avoid ice made from tap water, and be selective about raw fruits and vegetables that may have been washed in untreated water.
Swimming pool and recreational water safety deserves its own specific mention given how commonly it's overlooked. Because Giardia cysts tolerate normal chlorination levels far better than most pathogens, public health guidance for swimmers, particularly parents of young children, generally recommends taking children on frequent bathroom breaks during pool time, avoiding swallowing pool water altogether, and, especially important for anyone who has recently had a diarrheal illness of any kind, waiting a full two weeks after symptoms have completely resolved before returning to swim in a shared pool, since a person can continue shedding cysts for some time even after diarrhea itself has stopped. Public swimming facilities also generally ask that diapered children be changed away from the poolside rather than at deck level, specifically to reduce the chance of contaminating the surrounding pool area even before a child enters the water.
Frequently Asked Questions
Can Giardia go away on its own without treatment?
Occasionally, yes — some infections do resolve without specific treatment, particularly in otherwise healthy people, though this can take considerably longer than a treated course would and carries a higher risk of ongoing transmission to others in the meantime. Because effective treatment is short and well-tolerated, most providers recommend treating a confirmed infection rather than waiting for spontaneous resolution.
Is Giardia the same thing as "traveler's diarrhea"?
No, though it's one of the more common specific causes of it. Traveler's diarrhea is a broad, informal term covering diarrheal illness acquired during travel, which can be caused by various bacteria, viruses, or parasites including Giardia. A stool test is what actually identifies Giardia as the specific cause in any individual case, allowing treatment to be targeted appropriately rather than guessed at.
Can you get Giardia more than once?
Yes. Unlike some infections that confer lasting immunity, prior Giardia infection provides only partial and incomplete protection against future infection, meaning reinfection after a new exposure is entirely possible, even relatively soon after a previous, successfully treated episode, particularly if the new exposure involves a genetically distinct strain of the parasite.
Do I need a follow-up stool test after finishing treatment?
It depends on your situation. Providers commonly skip routine follow-up testing when symptoms fully resolve after a standard treatment course, but a follow-up test is generally recommended if symptoms persist, in certain higher-risk patients, or specifically to confirm clearance before returning to a setting like childcare work where transmission risk to others is a particular concern, or when a workplace or program specifically requires documented clearance before allowing someone to return.
Why did my test look for Giardia specifically instead of just "parasites" in general?
Newer stool antigen and molecular tests are often ordered as targeted panels checking for a handful of the most common and clinically significant organisms, including Giardia specifically, rather than the broader, more time-intensive traditional ova and parasite microscopy exam that screens more generally. Your provider's choice of test reflects which approach best fits your specific symptoms and history.
Can I catch Giardia from my pet dog or cat?
It's uncommon, though not entirely impossible. Genetic studies show the Giardia strains most frequently infecting dogs and cats generally differ from the strains most commonly found in humans, making pet-to-owner transmission considerably less likely than water-borne or person-to-person spread. Good hand hygiene after handling pet waste remains a reasonable precaution regardless.
Global public health surveillance data consistently ranks Giardia among the most commonly identified intestinal parasites worldwide, and its true prevalence is almost certainly higher than reported figures suggest, given how frequently the infection produces no symptoms at all and therefore never prompts testing in the first place. This widespread distribution, spanning both developing regions with limited water infrastructure and fully industrialized countries with modern sanitation systems alike, reflects just how effectively the parasite's low infectious dose and hardy cyst form allow it to persist across an enormous range of environmental and socioeconomic conditions, rather than being confined to any single type of setting or region.
Ultimately, understanding Giardia's biology, transmission patterns, and treatment options turns what can initially feel like an alarming, unfamiliar lab result into a straightforward, well-mapped clinical situation with a genuinely favorable outlook in the overwhelming majority of cases, regardless of how or where the original exposure happened.
Conclusion
Finding Giardia on a stool test is a common, well-understood result with a clear path forward: a short course of an effective antiparasitic medication resolves the vast majority of cases, and even the lingering symptoms some people experience afterward, like temporary lactose intolerance, are recognized, well-documented, and generally self-limited. Understanding the parasite's two-stage life cycle explains both how it spreads so effectively through water and close contact, and why a single stool sample doesn't always catch it on the first try. With that context, a positive result becomes a clearly actionable finding rather than a source of ongoing uncertainty.
Still Not Sure What Your Results Mean?
Upload your labs and get a complete, visual, plain-language interpretation of every biomarker — delivered to your inbox in under 15 minutes.
Get My ReportThis article is for educational purposes only and does not constitute medical advice. Always consult your healthcare provider regarding your specific lab results.