
Understanding What Leukocyte Esterase in Urine Indicates
Leukocyte esterase is one of the most commonly misunderstood lines on a urinalysis report, largely because it sounds like it's directly detecting an infection when it's actually doing something more specific and, in some ways, more indirect. This chemical test doesn't detect bacteria at all — it detects an enzyme released specifically by your own white blood cells, meaning a positive result is really a signal that your immune system has been activated in the urinary tract, not necessarily proof that bacteria caused that activation. Understanding this distinction changes how you should read a positive or negative result, why it's almost always paired with a separate test for nitrite, and why certain everyday factors can throw the result off in either direction. This article walks through exactly what leukocyte esterase is, how the dipstick actually detects it, and what a positive or negative finding genuinely does and doesn't tell you.
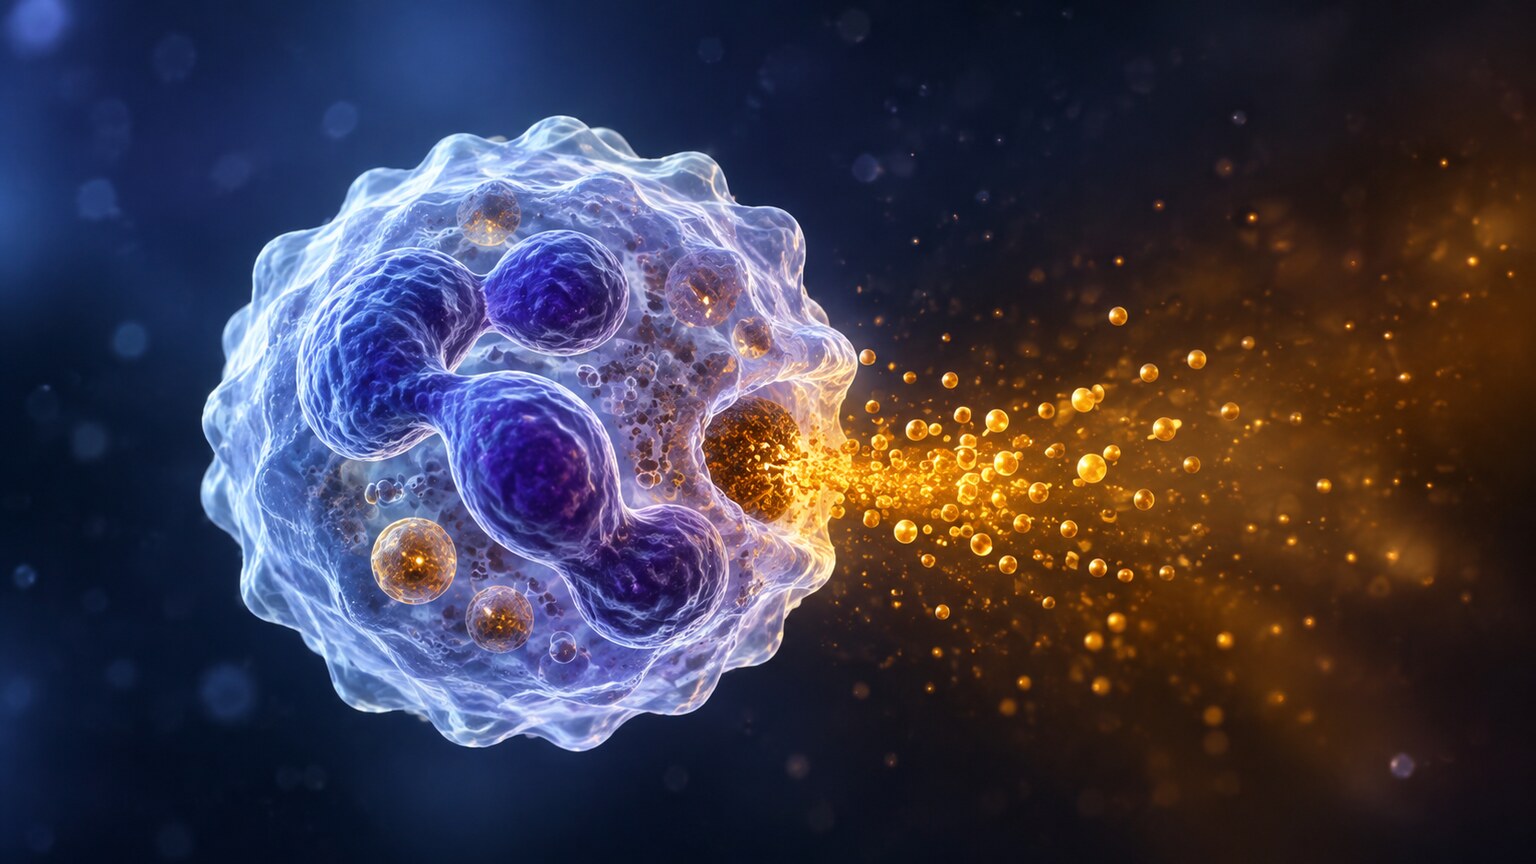
Figure 1. Leukocyte esterase is an enzyme stored inside granules within neutrophils, a type of white blood cell — when neutrophils are present and active in urine, they release this enzyme, which the dipstick test is specifically designed to detect.
Why a Urinalysis Bothers Checking for White Blood Cells at All
It helps to start with why this test exists in the first place. Under normal, healthy conditions, urine contains few if any white blood cells, since the urinary tract, from the kidneys down through the bladder and urethra, isn't an area where immune cells are routinely stationed the way they are in tissues more regularly exposed to the outside world, like skin or the lining of the gut. White blood cells only show up there in meaningful numbers when something has specifically called them in — an infection, an irritation, or an inflammatory process actively recruiting them to that specific location.
This is exactly what makes their presence, or the presence of the enzyme they release, such a useful piece of information: it's not a normal background finding that needs its own separate interpretation scale the way something like a hormone level might. It's closer to a binary signal — either the immune system has been activated in this specific location, or it hasn't — which is part of why even a fairly simple dipstick test can carry real diagnostic weight despite being far less sophisticated than many other laboratory tests, and why it remains a standard part of urinalysis panels decades after it was first introduced.
What Leukocyte Esterase Actually Is
Leukocyte esterase isn't a bacterial product, a waste product, or anything produced by the kidneys — it's an enzyme naturally stored inside specialized granules within neutrophils, the most abundant type of white blood cell and the immune system's primary first responders against infection. When neutrophils are recruited into the urinary tract in response to some kind of irritation, inflammation, or infection, some of them break down or actively release these granules, spilling leukocyte esterase into the surrounding urine, where it becomes detectable by a properly designed chemical test.
This is the single most important concept for correctly interpreting this test: a positive leukocyte esterase result is fundamentally a marker of white blood cell activity in the urinary tract, not a direct marker of bacteria themselves. In the large majority of cases, white blood cells show up in urine because bacteria are present and triggering an immune response, but the test itself is measuring the immune response, not the bacteria — a distinction that becomes clinically important in several specific scenarios covered later in this article.
Neutrophils are recruited to a site of potential infection through a well-studied signaling process: cells at the site of irritation or infection release chemical distress signals, and neutrophils circulating nearby in the bloodstream respond to these signals by squeezing through the walls of small blood vessels and migrating directly toward the source of the signal. Once they arrive at the urinary tract tissue, they begin their normal job of engulfing and destroying bacteria, a process that itself causes some of their internal granules, including the ones containing leukocyte esterase, to rupture or be actively released as part of this defensive activity.
This means the enzyme detected on a dipstick isn't simply leaking out passively — its release is tied directly to neutrophils actively doing their job, engaging with whatever they've identified as a threat. A higher leukocyte esterase reading generally reflects a larger number of neutrophils having been recruited and actively engaged in this process, which is part of why the semi-quantitative grading system described later carries real, meaningful clinical information rather than being an arbitrary scale.
Why Neutrophils Specifically, and Not Other White Blood Cells
It's worth understanding why this test is built around neutrophils specifically, rather than white blood cells in general, since the human body contains several different types of white blood cells with different specialized roles. Neutrophils happen to be both the most abundant type of white blood cell circulating in blood and the fastest-responding type recruited to a new site of bacterial infection, typically arriving within hours of an infection beginning, well before other, slower-responding immune cell types become involved in meaningful numbers.
Because neutrophils are both the dominant responder and the fastest to arrive in a typical bacterial urinary tract infection, they end up being, by a wide margin, the most common type of white blood cell found in urine during an active infection, which is exactly why a test built around detecting an enzyme specific to neutrophils captures the vast majority of clinically relevant cases. Other white blood cell types can appear in urine in certain, less common circumstances, but neutrophils' overwhelming numerical dominance during typical urinary tract infections is precisely why they became the natural target for this specific chemical test.
Curious what the rest of your urinalysis results are telling you? Upload your results and get a complete, plain-language breakdown in under 15 minutes.
Analyze My ResultsHow the Dipstick Actually Detects This Enzyme
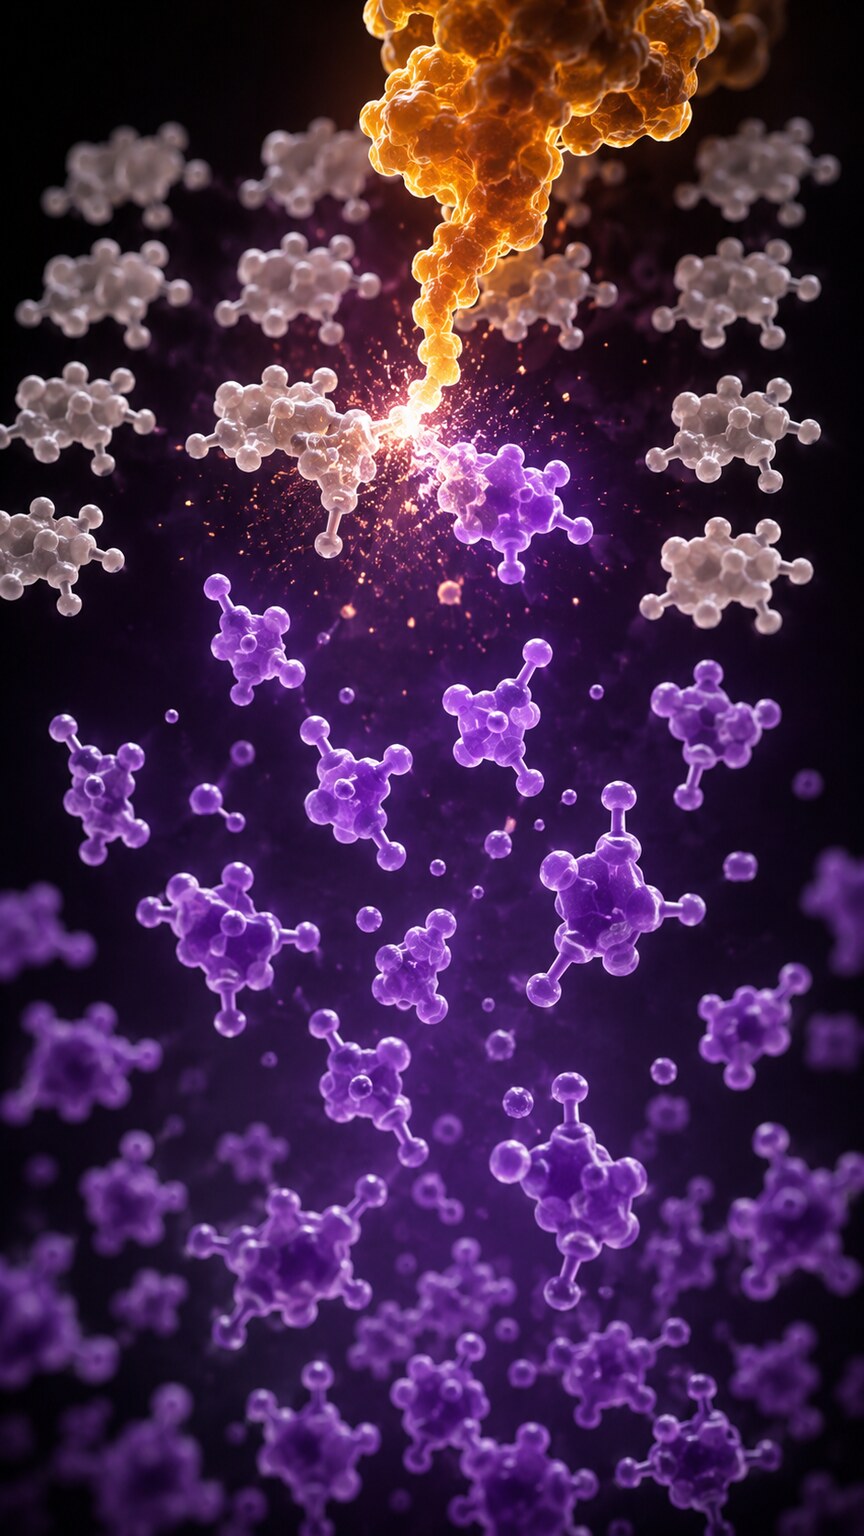
Figure 2. The dipstick pad is coated with a colorless chromogenic ester compound; leukocyte esterase chemically breaks this compound apart, releasing a separate dye molecule that turns the pad a visible purple color proportional to how much enzyme is present.
The dipstick pad specifically designed to detect leukocyte esterase is coated with a manufactured chemical compound called a chromogenic ester, engineered so that leukocyte esterase, and essentially nothing else commonly found in urine, is capable of breaking it apart. When the pad contacts urine containing this enzyme, the enzyme cleaves the ester bond in this compound, releasing a separate, previously bound dye molecule that then reacts with the surrounding chemistry on the pad to produce a visible purple color change.
The intensity and speed of this color change scale with how much active enzyme is actually present in the sample, which is why leukocyte esterase results are typically reported on a semi-quantitative scale — negative, trace, and then increasing grades often labeled 1+, 2+, and 3+ — rather than as a simple positive-or-negative flag. A higher grade generally suggests a larger number of white blood cells actively present and releasing this enzyme, though, as covered further below, the grade alone doesn't tell the complete story about what's actually causing that white blood cell activity.
This color-change reaction is read using one of two methods depending on the setting. In many clinics and smaller labs, a trained person reads the color visually, comparing the reacted pad against a printed reference chart showing the expected color at each grade, timed to a specific number of seconds after the strip contacts the sample, since the color continues to develop for a short period and reading it too early or too late can shift the apparent grade. Larger laboratories increasingly use automated strip-reading instruments instead, which use a calibrated light sensor to measure the exact color and intensity produced, removing the subjectivity of a visual read and improving consistency, particularly for results sitting near the boundary between two grades where a human reader's judgment might reasonably vary.
Timing sensitivity in this reaction is also worth understanding directly, since it explains a specific, correctable source of error. The chromogenic reaction needs a consistent, specified amount of time to fully develop before being read — reading it too early can understate a genuinely present enzyme level, since the color hasn't finished developing yet, while reading it too late can occasionally produce a color shift that overstates the result, since the reaction can continue to slowly progress or be affected by evaporation and other factors the longer the strip sits exposed. This is exactly why laboratory protocols specify an exact reading window, typically somewhere around one to two minutes after the strip contacts urine, and why deviations from that window are a genuine, documented source of result variability in real-world testing.
What a Trace Result Actually Means
A result reported as "trace," sitting between a clean negative and a full 1+ positive, deserves its own specific mention, since it's a genuinely ambiguous middle ground that causes real confusion. A trace result generally reflects a small but detectable amount of leukocyte esterase activity, corresponding to a modest number of white blood cells, below what would typically be considered clearly significant but above the level seen in someone with no white blood cell activity in their urine at all.
How much weight a trace result deserves depends heavily on the surrounding clinical picture. A trace result in someone with no urinary symptoms at all is often considered a nonspecific, low-significance finding, sometimes simply repeated on a later sample to see whether it persists, rises, or resolves. A trace result in someone with genuine, specific urinary symptoms — burning, urgency, frequency — carries considerably more weight and is more likely to prompt further testing or even empiric treatment, since a real, early-stage infection can sometimes present with a milder, trace-level dipstick finding rather than an unambiguous, strongly positive one, particularly very early in the course of infection before the immune response has fully ramped up.
Why Leukocyte Esterase and Nitrite Are Tested Together
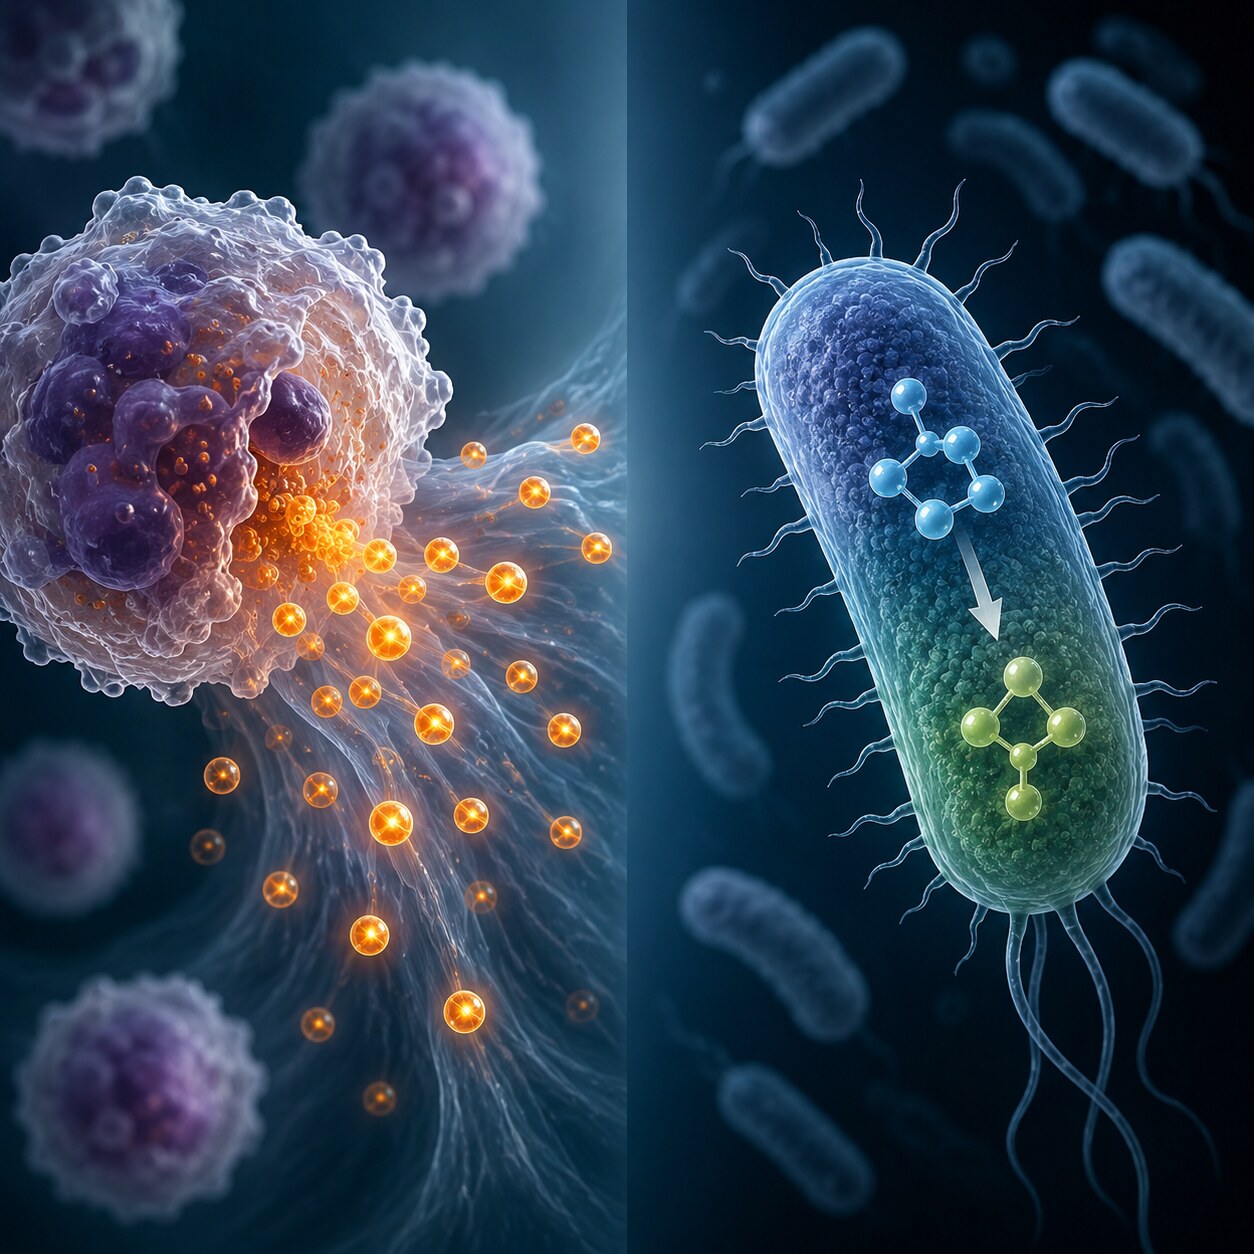
Figure 3. Leukocyte esterase and nitrite measure two fundamentally different things — one detects your own immune response, the other detects a specific chemical byproduct certain bacteria produce — which is exactly why testing both together provides more complete information than either alone.
A standard urinalysis dipstick almost always tests for leukocyte esterase and a separate marker called nitrite at the same time, and understanding why these two specific tests are paired together requires understanding that they're measuring two genuinely different sides of the same potential problem. Nitrite detects a specific chemical conversion that certain bacteria, though not all urinary pathogens, are capable of performing: converting nitrate, a substance normally present in urine from diet, into nitrite, a related but chemically distinct compound the dipstick is specifically built to detect.
Because leukocyte esterase measures the host's immune response and nitrite measures a specific bacterial chemical capability, combining both tests captures more of the overall picture than either one alone. A bacterium capable of producing nitrite but present in numbers too low to yet trigger a significant immune response might show a positive nitrite result with a negative or only trace leukocyte esterase result. Conversely, a bacterium incapable of producing nitrite at all, despite genuinely causing infection and triggering a real immune response, would show a positive leukocyte esterase result with a negative nitrite result. Testing both together substantially reduces the chance that either kind of infection slips through undetected by relying on just one marker alone.
It's worth being specific about why some bacteria can't produce nitrite at all, since this directly explains one of the two failure modes described above. The conversion of nitrate into nitrite requires a specific enzyme that only certain bacterial species happen to carry, most notably many of the gram-negative rod-shaped bacteria responsible for the large majority of urinary tract infections. Certain other bacteria capable of causing genuine urinary tract infections simply don't carry this particular enzyme, meaning their presence, no matter how numerous or how strong the resulting immune response, will never produce a positive nitrite result on its own. This is a structural, permanent limitation of the nitrite test for these specific organisms, not a matter of timing or sample quality the way some limitations of the leukocyte esterase test are.
Combining the four possible result patterns across both tests gives a useful mental framework for how a result is typically interpreted. Both markers positive is generally considered the strongest, most straightforward evidence pointing toward infection. Leukocyte esterase positive with nitrite negative still carries meaningful weight toward infection, particularly with accompanying symptoms, since it may simply reflect a nitrite-negative organism. Nitrite positive with leukocyte esterase negative or trace is a less common but recognized pattern, sometimes reflecting a very early infection where the immune response hasn't fully caught up yet. Both markers negative substantially lowers, though doesn't entirely eliminate, the likelihood of a urinary tract infection, particularly in someone with clear, specific symptoms, where further testing might still be pursued despite a negative dipstick.
None of these four patterns functions as an absolute, standalone rule in every situation — each one shifts the overall probability of infection up or down rather than delivering a guaranteed answer on its own, which is exactly why the complete clinical picture, not the dipstick pattern in isolation, ultimately drives the actual diagnostic and treatment decision a provider makes.
How Symptoms Change the Weight a Result Carries
Beyond the specific combination of dipstick findings, the presence or absence of actual symptoms meaningfully shifts how a given result should be interpreted, a principle that applies to leukocyte esterase just as much as it applies to other findings covered elsewhere in urinary diagnostics. A strongly positive leukocyte esterase result in someone with classic urinary symptoms — burning during urination, urgency, frequency — is generally treated as strong supporting evidence for infection, often enough on its own to justify starting treatment even before further confirmatory testing comes back.
The same strongly positive result in someone with no urinary symptoms at all tells a genuinely different story, and is treated with considerably more caution before jumping to a diagnosis or treatment decision. This is directly analogous to the concept of asymptomatic bacteriuria discussed in the context of urine cultures — a real, measurable finding that doesn't necessarily represent a condition requiring treatment, since the underlying inflammatory activity may reflect a resolving prior infection, an incidental, non-infectious cause, or simply enough contamination or nonspecific immune activity to trigger a positive reading without ongoing clinically significant illness.
This symptom-weighted approach reflects a broader, deliberate philosophy in how urinary findings are generally managed: the goal isn't to chase every abnormal chemical marker toward a treatment decision regardless of context, but to use each marker as one input feeding into a clinical judgment that ultimately depends on the whole picture a person presents with, not any single isolated number standing alone.
Positive Leukocyte Esterase Without a True Infection
Because leukocyte esterase fundamentally measures white blood cell activity rather than bacteria directly, several genuinely non-infectious situations can produce a positive result. Interstitial cystitis, a chronic bladder condition involving inflammation of the bladder wall without any active bacterial infection, can trigger enough white blood cell recruitment into the urinary tract to produce a positive leukocyte esterase reading despite no bacteria being present at all. Certain kidney stones can produce a similar irritation-driven inflammatory response as they move through or sit within the urinary tract, triggering white blood cell activity through mechanical irritation rather than infection.
Vaginal contamination is a particularly common, often overlooked source of a positive result in women specifically, since normal vaginal secretions can contain white blood cells of their own, especially during certain points in the menstrual cycle or in the presence of a vaginal infection entirely unrelated to the urinary tract. If a urine sample isn't collected using proper clean-catch technique, these vaginal white blood cells can contaminate the sample and produce a positive leukocyte esterase result that has nothing to do with the bladder or kidneys at all. This is exactly why a positive leukocyte esterase result in someone with no urinary symptoms sometimes prompts a recollection using more careful technique before drawing further conclusions.
Sexually transmitted infections represent another genuinely important non-bacterial-urinary-tract cause worth understanding specifically, since certain organisms responsible for common sexually transmitted infections can trigger inflammation and white blood cell recruitment in the urethra itself, producing a positive leukocyte esterase result through a mechanism entirely separate from the classic bladder-ascending route covered throughout the rest of this article. This is one of the more clinically important reasons a positive leukocyte esterase result, particularly in a sexually active person without the classic combination of bladder-specific symptoms, sometimes prompts specific testing for sexually transmitted infections alongside, or instead of, a standard urine culture.
This urethral-versus-bladder distinction matters clinically because the two situations, despite producing an identical positive dipstick finding, call for genuinely different follow-up testing and, ultimately, different treatment. A classic ascending bladder infection is generally addressed with a standard urine culture and antibiotic course, whereas a urethral inflammation driven by a sexually transmitted organism requires a specific test targeted to that particular organism, since standard urine culture techniques aren't designed to detect it. Recognizing which pattern of symptoms points toward each scenario is exactly what allows a clinician to choose the right follow-up test rather than defaulting to the same standard workup regardless of the actual underlying cause.
Catheter use introduces its own distinct, mechanical source of a positive result. A catheter is, by necessity, a foreign object sitting inside the urinary tract, and its mere physical presence can cause a low-grade, ongoing irritation of the surrounding tissue, recruiting some baseline level of white blood cells even in the complete absence of any bacterial infection. This is part of why interpreting leukocyte esterase results in someone with a long-term indwelling catheter is considerably more nuanced than in someone without one — some degree of positivity is essentially an expected baseline finding tied to the catheter's presence itself, meaning a genuinely new infection in this population is more reliably identified by a change from that person's own established baseline pattern than by the simple presence of any positivity at all.
Pregnancy and Other Situations Where Interpretation Shifts
Pregnancy introduces its own specific wrinkle to how leukocyte esterase results are interpreted, tied closely to the asymptomatic bacteriuria concept mentioned earlier. Because bacteriuria during pregnancy carries documented risks to both mother and baby even without symptoms, providers generally interpret urinary findings, including leukocyte esterase, with a lower threshold for further investigation during pregnancy than they would apply to the same finding in a non-pregnant person. A result that might be observed and simply monitored in a non-pregnant adult is more likely to prompt an actual urine culture and, if confirmed, treatment during pregnancy specifically.
Children represent another population where interpretation shifts somewhat, partly because collecting a clean, uncontaminated urine sample is considerably more difficult in young children who aren't yet toilet-trained, raising the baseline likelihood that a positive result reflects contamination rather than true urinary tract involvement. This is part of why specific, more controlled collection methods are sometimes used in young children specifically to obtain a more reliable sample before drawing conclusions from a leukocyte esterase result that might otherwise carry higher uncertainty than the same result in an adult who can provide a properly collected, clean-catch sample without difficulty.
Older adults represent yet another population where a positive result deserves particular care in interpretation, given the notably high prevalence of asymptomatic bacteriuria in this group discussed in related contexts elsewhere. A positive leukocyte esterase finding discovered incidentally in an older adult being evaluated for an unrelated reason is generally not treated as an automatic call to action on its own, precisely because this population shows such a high baseline rate of positive urinary findings without any accompanying acute illness requiring intervention, a pattern well documented enough that specific guidelines exist cautioning against reflexive testing or treatment based purely on this finding in this specific age group.
What Can Cause a False Negative Despite Real Infection

Figure 4. Testing a urine sample promptly after collection matters mechanically, since white blood cells begin breaking down over time once outside the body, meaning a delayed or improperly stored sample can produce a falsely negative leukocyte esterase result even when real infection is present.
Just as certain factors can produce a false positive, others can mask a genuine infection and produce a false negative. Highly concentrated glucose in the urine, high levels of protein, or an unusually high concentration of certain other substances can interfere with the dipstick's chemical reaction, dampening the color change even when leukocyte esterase is genuinely present. High-dose vitamin C, a strong reducing agent, is a particularly well-documented interferent capable of suppressing this specific chemical reaction, occasionally masking a real positive result in someone taking substantial vitamin C supplements.
Timing and sample handling matter mechanically as well. White blood cells are living cells that begin breaking down once outside the body, and this breakdown accelerates the longer a sample sits before being tested, particularly at room temperature. A urine sample left standing too long before testing can show falsely low or even negative leukocyte esterase despite white blood cells having genuinely been present in significant numbers at the moment of collection, which is exactly why prompt testing, ideally within about an hour of collection, or proper refrigeration if testing must be delayed, is a standard part of accurate urinalysis technique.
Highly dilute urine, produced after drinking a large volume of fluid shortly before providing a sample, introduces a related but mechanistically distinct problem. Rather than degrading the enzyme itself, dilution simply spreads whatever white blood cells and enzyme are genuinely present across a larger volume of fluid, lowering their effective concentration below what the dipstick's fixed sensitivity threshold requires to register a clear positive result, even though the total number of white blood cells produced by the body's immune response hasn't actually decreased. This is part of why some testing protocols specifically recommend using a first-morning urine sample when possible, since urine produced overnight is naturally more concentrated, having had many hours to accumulate without the diluting effect of recent fluid intake, giving the dipstick reaction the best possible chance of accurately reflecting what's genuinely present.
Certain antibiotics, when a person has already begun treatment before a urinalysis is performed, can also blunt a leukocyte esterase result, since effective antibiotic treatment begins reducing the underlying bacterial burden and the resulting immune response relatively quickly, sometimes within the first day or two of treatment. This is part of why a urinalysis performed to confirm a suspected infection is generally most informative when collected before any antibiotic treatment has begun, rather than after treatment is already underway, since treatment itself can start moving the result toward negative independent of whether the original infection was ever fully confirmed through testing.
Why a Positive Dipstick Often Leads to a Microscopic Exam
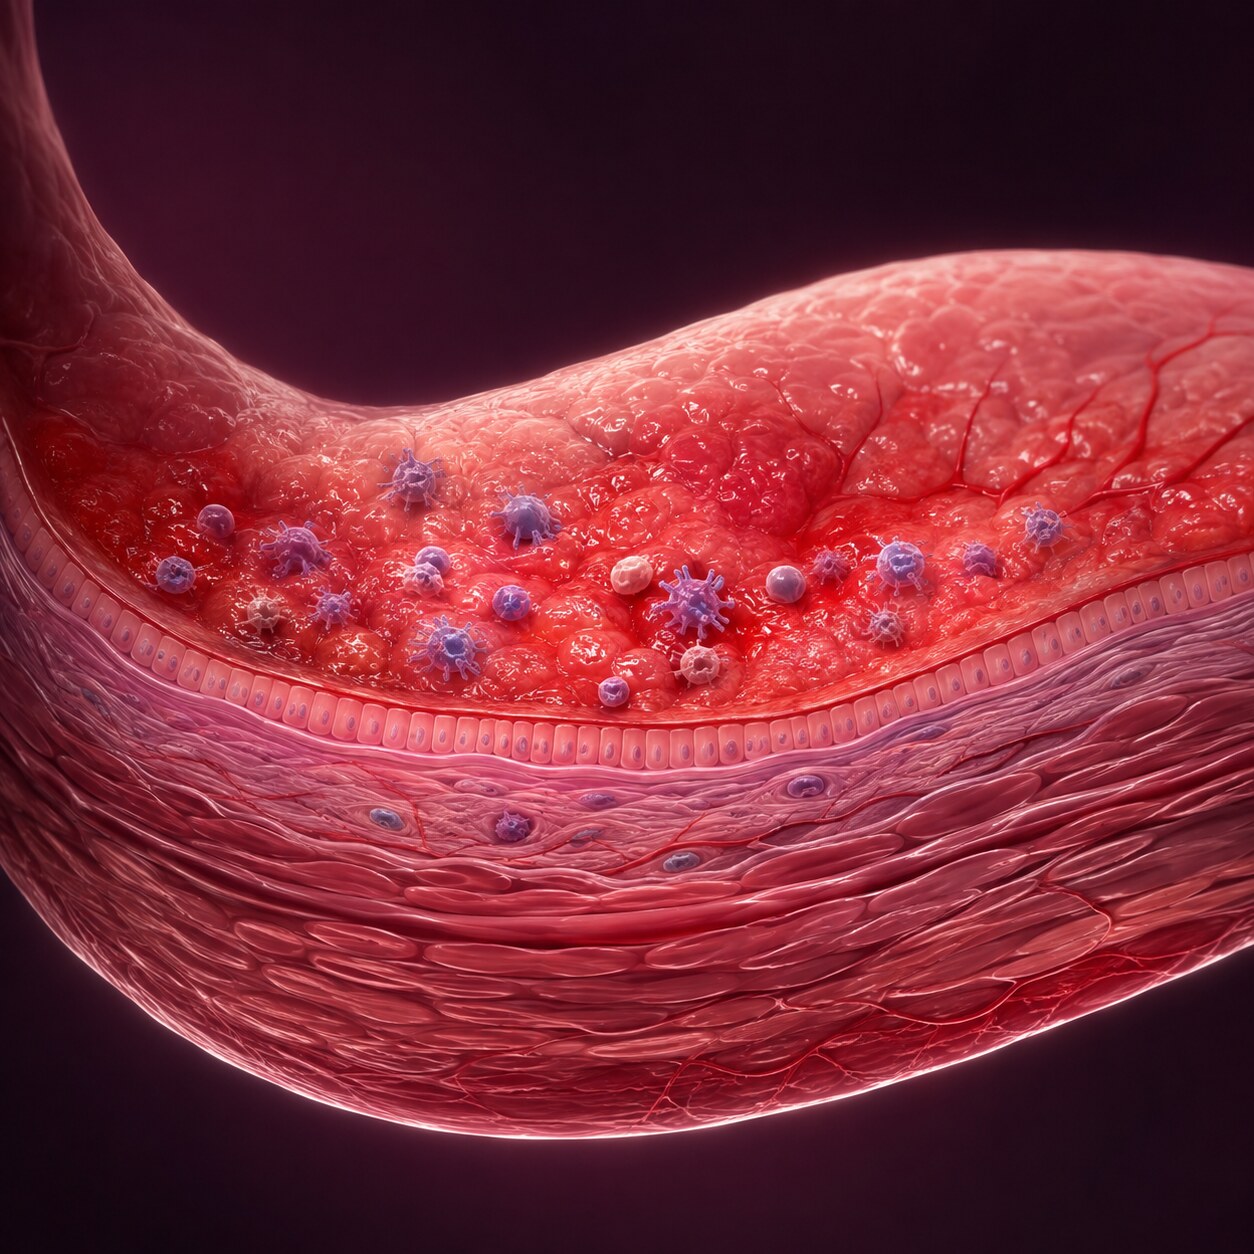
Figure 5. Conditions like interstitial cystitis can recruit white blood cells into the bladder and trigger a positive leukocyte esterase result through inflammation alone, entirely independent of any bacterial infection being present.
Because the dipstick chemical reaction is a useful but indirect proxy for actual white blood cell numbers, a positive leukocyte esterase result, particularly one that seems inconsistent with the rest of the clinical picture, is often followed up with a direct microscopic examination of the urine sample. Under the microscope, a laboratory technician can directly count the actual number of white blood cells present per high-power field, providing a more precise, direct confirmation than the chemical proxy test alone can offer.
This microscopic count also allows a technician to look for additional context the dipstick alone can't provide, such as whether the white blood cells appear alongside visible bacteria, red blood cells, or other specific cellular elements that might point toward one underlying cause over another. This combination of a fast chemical screening test followed by a more detailed microscopic confirmation, when needed, mirrors a broader pattern common across laboratory medicine: a quick, sensitive initial test flags a possible concern, and a slower, more specific test confirms exactly what's actually going on before a final clinical decision is made.

Figure 6. A direct microscopic count of white blood cells provides confirmation the chemical dipstick reaction alone can't offer, since it measures the cells themselves rather than relying on the enzyme they release as an indirect proxy.
The two tests aren't always in perfect agreement, and understanding why is itself informative. A dipstick can show a strongly positive leukocyte esterase reading while a microscopic count comes back with relatively few visible white blood cells, particularly if the sample sat for a while before the microscopic portion was performed, since, as covered earlier, white blood cells break down over time in ways that can sometimes still leave enough residual enzyme activity to register on the chemical test even after the intact cells themselves are no longer easily countable under the microscope. This kind of discrepancy is part of why an experienced clinician weighs both results together, alongside symptoms and other findings, rather than treating either test as the single, final word on its own.
The reverse mismatch, a relatively modest dipstick reading alongside a genuinely elevated microscopic white blood cell count, can also occur, sometimes reflecting neutrophils that have been recruited to the area but haven't yet released a large amount of their internal enzyme content, an earlier stage in the same overall inflammatory process the dipstick is designed to detect further along. Recognizing that these two tests are measuring subtly different aspects of the same underlying biological event, rather than being two interchangeable methods of measuring the identical thing, helps explain why an occasional mismatch between them isn't a sign that either test is unreliable, but simply a reflection of the specific stage or dynamics of the process each one happens to be capturing at that particular moment.
Taken together, these various interfering factors are exactly why a single leukocyte esterase result, read in isolation from the collection conditions and clinical context surrounding it, is rarely treated as a fully sufficient basis for a diagnosis on its own — a theme that runs consistently through nearly every scenario covered in this article, from contamination to timing to the presence or absence of symptoms.
Frequently Asked Questions
Does positive leukocyte esterase always mean I have a UTI?
Not necessarily. It specifically indicates white blood cell activity in the urinary tract, which is commonly caused by bacterial infection but can also result from non-infectious inflammation, certain kidney stones, or contamination from vaginal secretions during sample collection.
Why does my urinalysis test for both leukocyte esterase and nitrite?
They measure two different things: leukocyte esterase detects your immune response, while nitrite detects a specific chemical byproduct certain bacteria produce. Testing both together captures a more complete picture than relying on either single marker alone.
Can vitamin C affect my leukocyte esterase result?
Yes. High-dose vitamin C can interfere with the dipstick's chemical reaction and suppress the color change, occasionally masking a genuinely positive result, particularly in people taking substantial vitamin C supplements.
Why would my doctor order a microscopic exam after a positive dipstick?
A microscopic exam directly counts white blood cells rather than relying on the dipstick's indirect chemical reaction, providing more precise confirmation and additional context, such as whether bacteria or other cells are visible alongside the white blood cells.
Should I collect a first-morning urine sample for the most accurate result?
It can help. Overnight urine is naturally more concentrated, giving the dipstick a better chance of detecting leukocyte esterase at a level above its fixed sensitivity threshold, compared to a more diluted sample collected after drinking a lot of fluid recently.
Is leukocyte esterase interpreted differently in someone with a long-term catheter?
Yes. A catheter's physical presence can cause a baseline level of irritation and white blood cell recruitment on its own, so some degree of positivity is often expected. A genuinely new infection is more reliably identified by a change from that person's own established baseline than by any positivity alone.
Conclusion
Leukocyte esterase is a chemical proxy for your own immune system's activity in the urinary tract, not a direct test for bacteria — an enzyme released by white blood cells that a specially designed dipstick reagent is built to detect through a specific color-producing chemical reaction. Because it measures inflammation rather than infection directly, a positive result can appear without true infection, and a genuine infection can occasionally produce a falsely negative result depending on sample handling and interfering substances. Understanding this distinction, and why it's always interpreted alongside nitrite and the broader clinical picture, is exactly what turns this single line on a urinalysis report from a confusing chemical marker into a genuinely informative piece of your overall results.
This same underlying principle — that a lab test frequently measures the body's own response to a problem rather than the problem itself — shows up repeatedly across many other areas of laboratory medicine, and recognizing it here provides a genuinely useful template for reading other, similarly indirect markers encountered elsewhere. A result is rarely a simple yes-or-no verdict on its own; it's a piece of evidence that becomes genuinely meaningful once placed alongside the specific mechanism producing it, the collection conditions, and the symptoms, or lack of symptoms, accompanying it.
Keeping that broader framing in mind is what ultimately turns any single line on a urinalysis report, leukocyte esterase included, from an intimidating, unfamiliar term into a genuinely understandable piece of information about what your own body is actually doing, rather than a cryptic result that raises more questions than it answers.
Still Not Sure What Your Results Mean?
Upload your labs and get a complete, visual, plain-language interpretation of every biomarker — delivered to your inbox in under 15 minutes.
Get My ReportThis article is for educational purposes only and does not constitute medical advice. Always consult your healthcare provider regarding your specific lab results.