
What's the Connection Between Magnesium and Sleep Quality?
Magnesium's popular reputation as a general "relaxation mineral" makes it sound like a vague, unfalsifiable wellness claim, the kind of thing repeated often enough to feel true without anyone actually explaining why — but the real mechanism behind it turns out to be specific, well-documented, decades-old neuroscience: magnesium directly controls how easily a particular brain receptor lets your nervous system power down at night. It isn't a sedative in any pharmacological sense, and it genuinely doesn't knock anyone out the way a sleeping pill would — instead, it regulates the actual biological gate your brain relies on to shift, gradually and naturally, from active, alert daytime signaling into the considerably quieter neural state that genuine, restorative sleep actually requires from start to finish. This article walks through that specific receptor mechanism in real detail, three additional distinct biological pathways magnesium influences that are genuinely relevant to sleep, and why a real, meaningful magnesium deficiency can end up disrupting sleep quality in ways that look and feel noticeably different from ordinary, everyday insomnia.
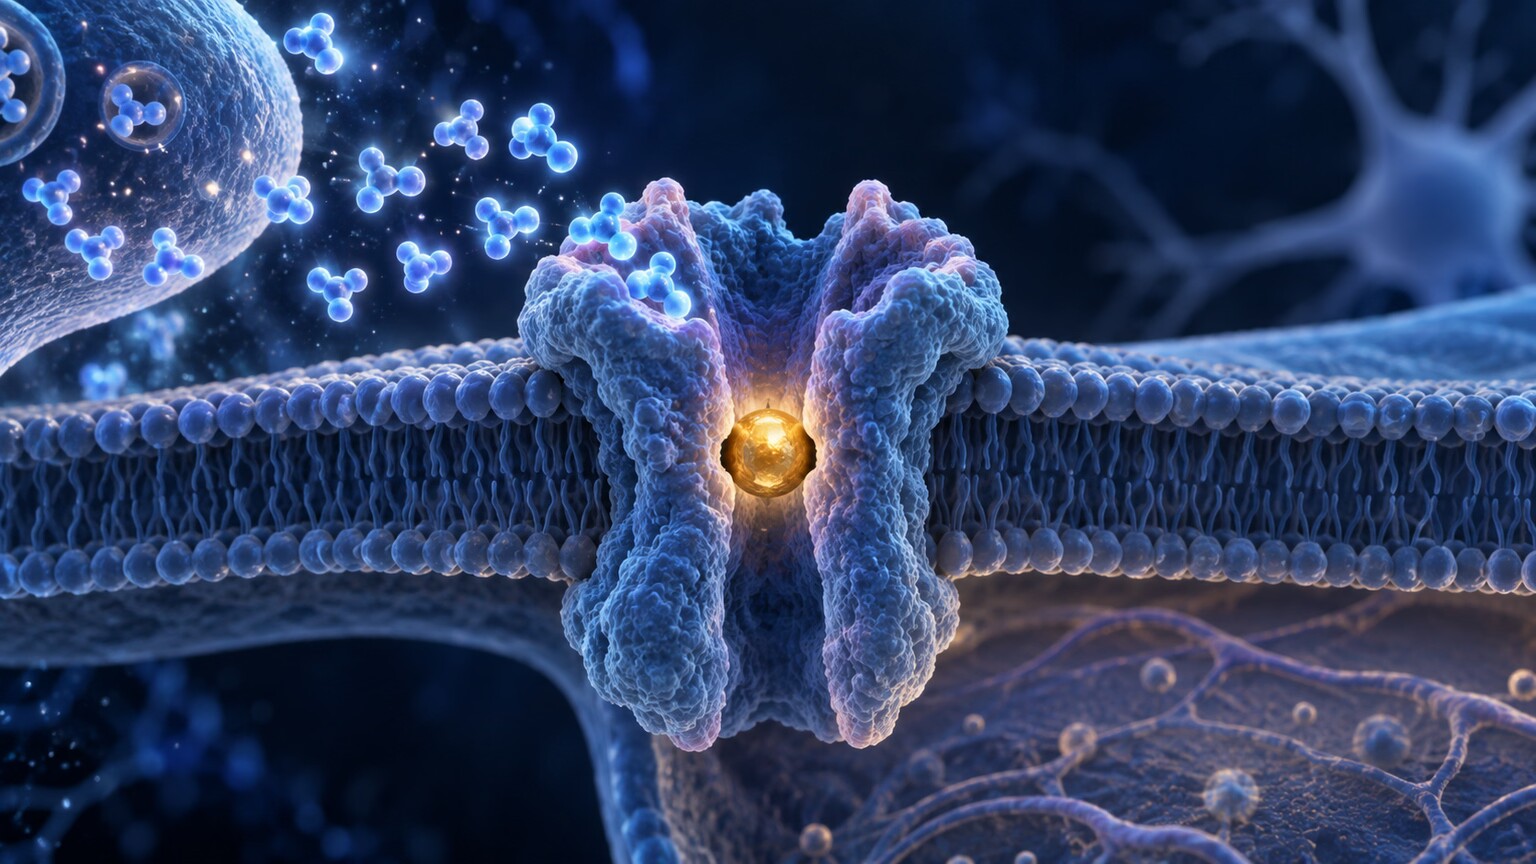
Figure 1. Magnesium ions physically plug the NMDA receptor channel, blocking excess excitatory signaling and allowing the nervous system to shift toward the quieter state needed for sleep onset.
The NMDA Receptor: Magnesium's Literal Gatekeeping Role
The true centerpiece of magnesium's entire connection to sleep, and arguably the single most important detail in this whole article, is a specific receptor found throughout the brain called the NMDA receptor, one of the primary channels through which the excitatory neurotransmitter glutamate does its work — glutamate being the brain's main "go" signal, driving alertness, learning, and active neural firing. Under ordinary, normal resting conditions, a single magnesium ion sits lodged directly inside the NMDA receptor's own physical channel, blocking it much like a cork sitting snugly inside the neck of a bottle, effectively preventing the channel from opening even in moments when glutamate is genuinely present nearby and actively attempting to activate that same receptor. This is genuinely not a side effect, a coincidence, or a minor secondary function — it's magnesium's specific, precisely well-characterized job at this exact receptor, first discovered several decades ago through careful electrophysiology research, and now considered one of the truly foundational, textbook pieces of basic neuroscience taught to students worldwide.
When magnesium is adequately available, this blocking effect keeps excitatory signaling in check by default, requiring a genuinely strong activating signal to dislodge the magnesium ion and let the channel open. When magnesium levels run low, fewer receptors have this protective plug in place, meaning excitatory signaling throughout affected regions of the brain can fire noticeably more easily, and considerably more often, than it genuinely should under otherwise normal, well-regulated circumstances. Applied to sleep specifically, this translates into a nervous system that has a harder time settling down at night, since the receptor-level brake that normally makes it more difficult to trigger excitatory firing is less consistently engaged.
It helps to understand why this particular receptor, out of the dozens of different receptor types in the brain, is so specifically tied to sleep and magnesium's action. NMDA receptors are unusually central to a property neuroscientists call synaptic plasticity — the strengthening and adjusting of connections between neurons that underlies learning, memory consolidation, and the brain's ongoing capacity to adapt its own wiring. This same plasticity-related activity runs at a naturally higher level during wakefulness, when the brain is actively processing new information, and needs to wind down considerably as sleep approaches for the transition into rest to happen smoothly. Because magnesium's blocking effect at this exact receptor is voltage-dependent — meaning it's most effective precisely when the surrounding neuron is in a relatively resting, less-excited electrical state — the mechanism is almost perfectly suited to reinforcing an already-quieting nervous system rather than working against an actively firing one, which is part of why magnesium's effect here is described as supportive and permissive rather than forceful or sedating.
Research using direct measurements of magnesium's effect on this receptor has also found that the blocking action isn't simply on-or-off — it operates along a graded continuum depending on exactly how much magnesium is available in the immediate vicinity of the receptor. This graded quality helps explain why magnesium's contribution to sleep tends to show up as a general shift in ease and depth of settling down, rather than a sharp, all-or-nothing switch between "awake" and "asleep." A modest reduction in available magnesium doesn't necessarily eliminate the blocking effect outright; it simply makes the receptor's channel somewhat easier to open than it would otherwise be, nudging the overall balance of excitatory and inhibitory signaling in a direction that makes settling into rest measurably harder, without necessarily preventing sleep altogether.
GABA: Magnesium's Second, Complementary Pathway
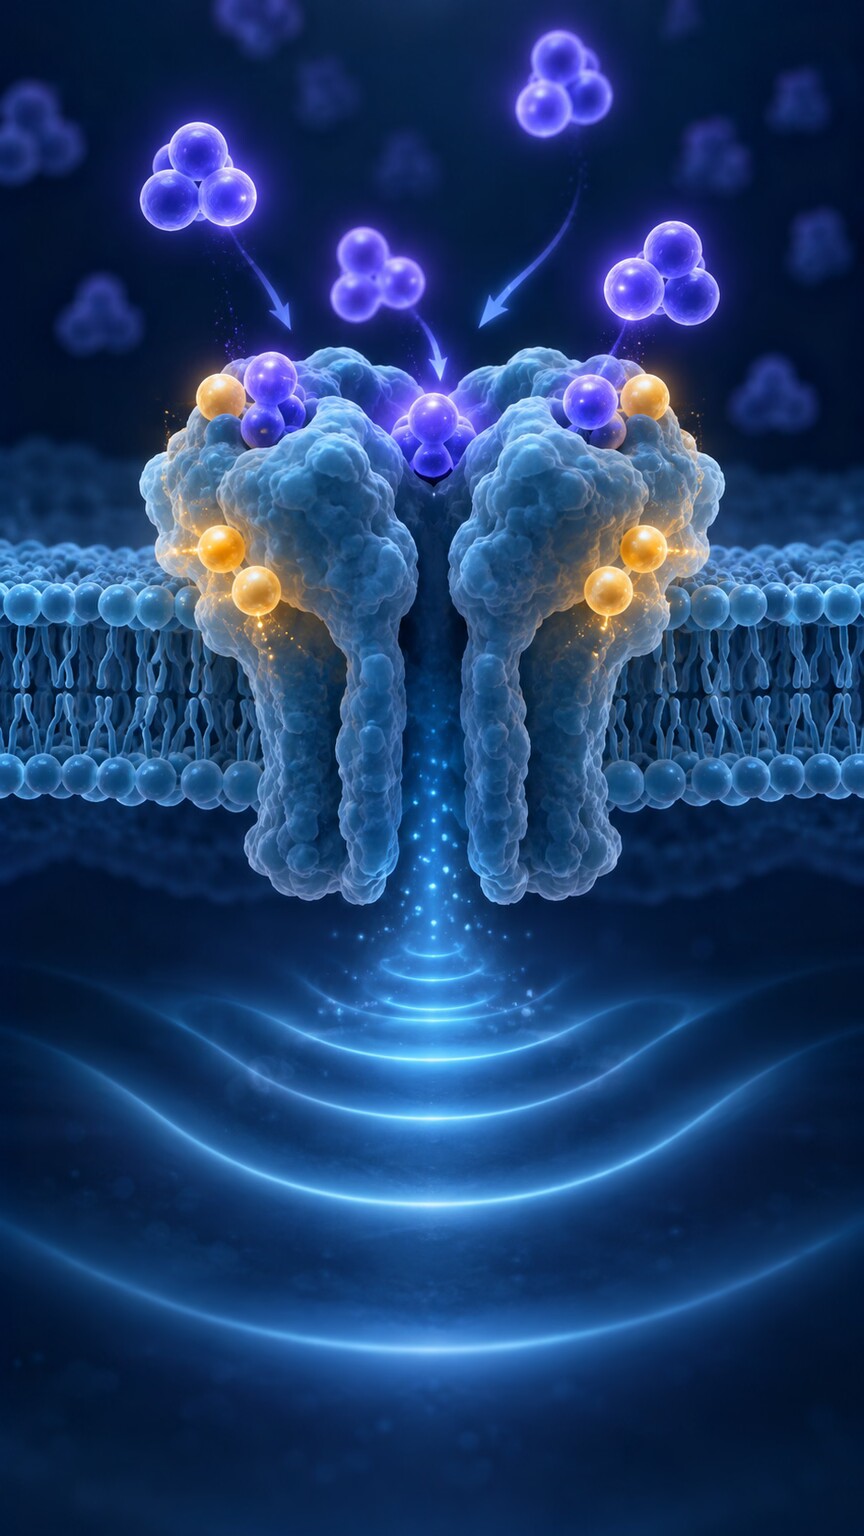
Figure 2. Magnesium supports GABA receptor function, the brain's primary inhibitory signaling system, working alongside the NMDA blocking effect to shift overall brain activity toward a calmer state.
Magnesium's second major, genuinely relevant role involves GABA specifically, widely recognized as the brain's primary inhibitory neurotransmitter overall — essentially the direct counterpart to glutamate's excitatory "go" signal, functioning essentially as the brain's main biological "stop" or "calm down" signal instead, operating in near-constant tension with glutamate's opposing effect. GABA itself works specifically by binding to its own dedicated set of receptors, and a body of research has consistently found that magnesium supports and meaningfully enhances how effectively these particular GABA receptors ultimately function, directly helping that inhibitory signal actually go on to produce its intended calming effect at the individual cellular level. Some of the most common active ingredients in over-the-counter sleep aids and prescription sedatives, including benzodiazepines, work specifically and directly by enhancing this exact same GABA receptor system — meaning magnesium is operating on a genuinely relevant, well-established piece of the same sleep-regulation architecture, just through a milder, cofactor-support role rather than a direct pharmacological one.
Together, these two mechanisms — blocking excess glutamate excitation at the NMDA receptor, and supporting the GABA system's calming inhibitory signal — describe a coordinated two-sided effect: magnesium simultaneously turns down the brain's "go" signal and supports its "stop" signal, rather than working through only one side of that balance. This dual mechanism is part of why magnesium's effect on sleep, in the research literature, is generally described as making the nervous system more capable of downshifting into rest, rather than acting as a direct sedative that forces sleep onset the way some medications do.
It's worth understanding specifically why GABA receptors respond the way they do to magnesium's presence, since the mechanism is somewhat different from the direct channel-blocking action described for NMDA receptors above. Rather than physically plugging the GABA receptor's channel, magnesium appears to influence the receptor's overall structural stability and its sensitivity to GABA itself, essentially making the receptor a more efficient, responsive receiver of the calming signal GABA is trying to send. Some research has specifically examined a subtype of GABA receptor believed to be particularly important for the deeper, more restorative stages of sleep, finding that magnesium availability influences how readily this specific receptor type responds — a detail that helps connect magnesium status not just to whether someone falls asleep, but potentially to the quality and depth of the sleep that follows.
This GABA-supporting role also helps explain a commonly reported experience worth addressing directly: many people describe magnesium supplementation as producing a subtle, gradual sense of calm rather than an immediate, noticeable sedative effect, and some report needing several days to a few weeks of consistent intake before noticing any change in their sleep at all. This gradual onset is consistent with a cofactor-support mechanism working on receptor sensitivity and overall nervous system balance, rather than a fast-acting pharmacological effect — magnesium isn't introducing a new calming signal from outside, it's supporting the body's own existing GABA system to work somewhat more effectively than it otherwise would, a subtler and slower kind of change than directly activating a receptor from scratch the way many sedative medications do.
Curious what your own magnesium level or other lab results actually mean? Upload your results and get a complete, plain-language breakdown in under 15 minutes.
Analyze My ResultsMelatonin: A Third, Separate Pathway Worth Distinguishing
A third mechanism, distinct from the two receptor-level effects above, involves melatonin, the hormone most directly associated with signaling to the body that it's nighttime. Magnesium serves as a required cofactor for an enzyme involved in melatonin's production pathway, meaning adequate magnesium is part of what allows the body to synthesize melatonin normally in the first place. This is a genuinely separate mechanism from the NMDA and GABA effects described above — one is about receptor-level excitability in the moment, the other is about whether the raw material for the body's own nighttime signaling hormone gets built adequately at all. Some research has also found that magnesium supplementation modestly increases circulating melatonin levels, though the research base here is less extensive than the well-established NMDA and GABA mechanisms, and melatonin production is influenced by many other factors — light exposure being the dominant one — meaning magnesium status is a contributing piece of this picture, not the primary driver of melatonin's daily rhythm.
The specific enzyme magnesium supports in this pathway operates near the end of a multi-step biochemical conversion process, transforming an intermediate compound into melatonin itself inside a small gland deep in the brain. Because this enzymatic step depends on magnesium as a required cofactor — meaning the enzyme genuinely cannot complete this specific chemical conversion efficiently without adequate magnesium present — a meaningful magnesium shortfall could theoretically create a bottleneck at this exact step in the pathway, even if every other input needed for melatonin production, including appropriate darkness and normal circadian signaling, is otherwise functioning correctly. This is a useful, concrete illustration of a broader pattern seen throughout human biochemistry: magnesium serves as a required cofactor for several hundred different enzymatic reactions throughout the body, and melatonin synthesis happens to be one of the more sleep-relevant examples of this general dependency.
It's worth being precise about what current research does and doesn't establish here, since melatonin is often discussed with more certainty than the underlying evidence fully supports. Several studies have found modest increases in circulating melatonin following magnesium supplementation in specific populations, including some studies conducted in older adults, a group in which both magnesium status and natural melatonin production tend to decline with age. However, the effect sizes reported have generally been more modest than the effects seen for the NMDA and GABA receptor mechanisms, and melatonin production is influenced by numerous other factors — light exposure timing being by far the dominant regulator, followed by age, and individual variation in the body's internal circadian clock — meaning magnesium's contribution here should be understood as one input among many rather than a primary lever for melatonin production on its own.
Cortisol and the Stress-Response Connection
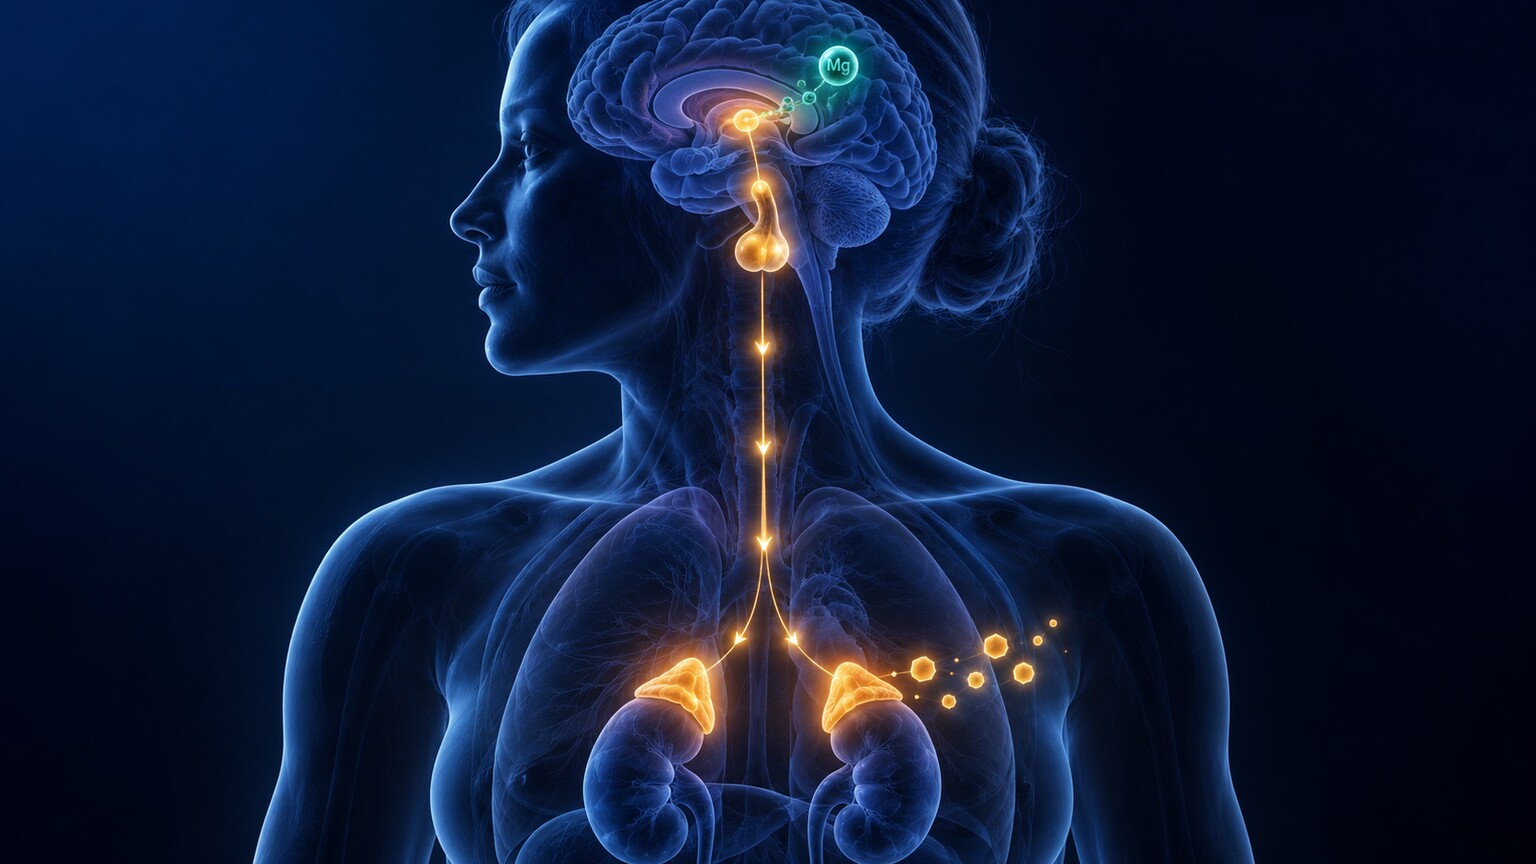
Figure 3. Magnesium helps regulate the HPA axis, the body's central stress-response system, and low magnesium is associated with elevated cortisol — a hormone that directly interferes with sleep onset when chronically raised.
A fourth pathway connects magnesium to the body's central stress-response system, called the HPA axis (hypothalamic-pituitary-adrenal axis), which governs the release of cortisol, the body's primary stress hormone. Magnesium plays a regulating role in this system, and research has found that magnesium deficiency is associated with an overactive HPA axis and correspondingly elevated cortisol levels. This matters directly for sleep because cortisol normally follows a specific daily rhythm — highest in the morning to promote alertness, lowest at night to allow sleep — and chronically elevated cortisol, particularly in the evening when it should be tapering off, is well documented to interfere with both falling asleep and staying asleep through the night.
This creates a specific, somewhat self-reinforcing pattern worth understanding: chronic stress itself depletes magnesium (through mechanisms including increased urinary magnesium excretion during sustained stress responses), and the resulting lower magnesium level then reduces the body's ability to properly regulate the same stress-response system, potentially allowing cortisol to run higher than it otherwise would. This is a distinct mechanism from the direct NMDA and GABA receptor effects described earlier — it's an indirect, hormonal pathway rather than a direct neurotransmitter effect, but it converges on the same practical outcome of harder, less restful sleep.
The specific way magnesium loss occurs during stress is worth understanding, since it's a genuinely direct physiological consequence rather than a vague association. When the HPA axis activates during a stress response, one of its downstream effects includes signaling the kidneys to excrete more magnesium in urine than they normally would, actively drawing down the body's available magnesium as part of the broader stress-response cascade. This means an episode of significant stress doesn't just feel mentally taxing — it has a measurable, direct effect on magnesium balance through kidney handling, distinct from any change in dietary intake during that same period. Chronic, ongoing stress compounds this effect by keeping this excretion pathway more consistently active over time, gradually drawing down magnesium reserves in a way that a single, brief stressful event wouldn't produce on its own.
This mechanism also helps explain a pattern many people recognize anecdotally but may not connect to magnesium specifically: periods of sustained high stress — a demanding work deadline, a family crisis, an extended period of poor sleep itself — often coincide with a noticeable worsening in sleep quality that persists even once the acute stressor has technically passed. Given the mechanism described here, this makes physiological sense: the elevated magnesium excretion during the stressful period may have meaningfully depleted available magnesium, and that depletion doesn't necessarily reverse the moment the external stressor resolves — restoring adequate magnesium status, whether through diet or supplementation, generally takes time, meaning the sleep disruption can meaningfully outlast the original stressful event itself.
The cortisol side of this pathway deserves its own closer look, since cortisol's relationship to sleep is more specific than simply "stress hormones are bad for sleep" suggests. Cortisol naturally follows a pattern called the diurnal cortisol rhythm — a sharp rise shortly after waking (sometimes called the cortisol awakening response), a gradual decline throughout the day, and a low point in the evening and overnight that's specifically necessary for normal sleep architecture to unfold correctly. Elevated evening cortisol, the specific pattern associated with a poorly regulated HPA axis, has been directly linked in research to both longer time needed to fall asleep and more fragmented, lighter sleep with reduced time spent in the deeper sleep stages considered most physically restorative. Magnesium's regulatory role in keeping the HPA axis appropriately responsive, rather than chronically overactive, is therefore relevant specifically to this evening cortisol pattern, not to cortisol's morning rise, which serves an entirely different and genuinely necessary purpose in promoting daytime alertness.
Muscle Relaxation: The Mechanism Behind the Common Claim
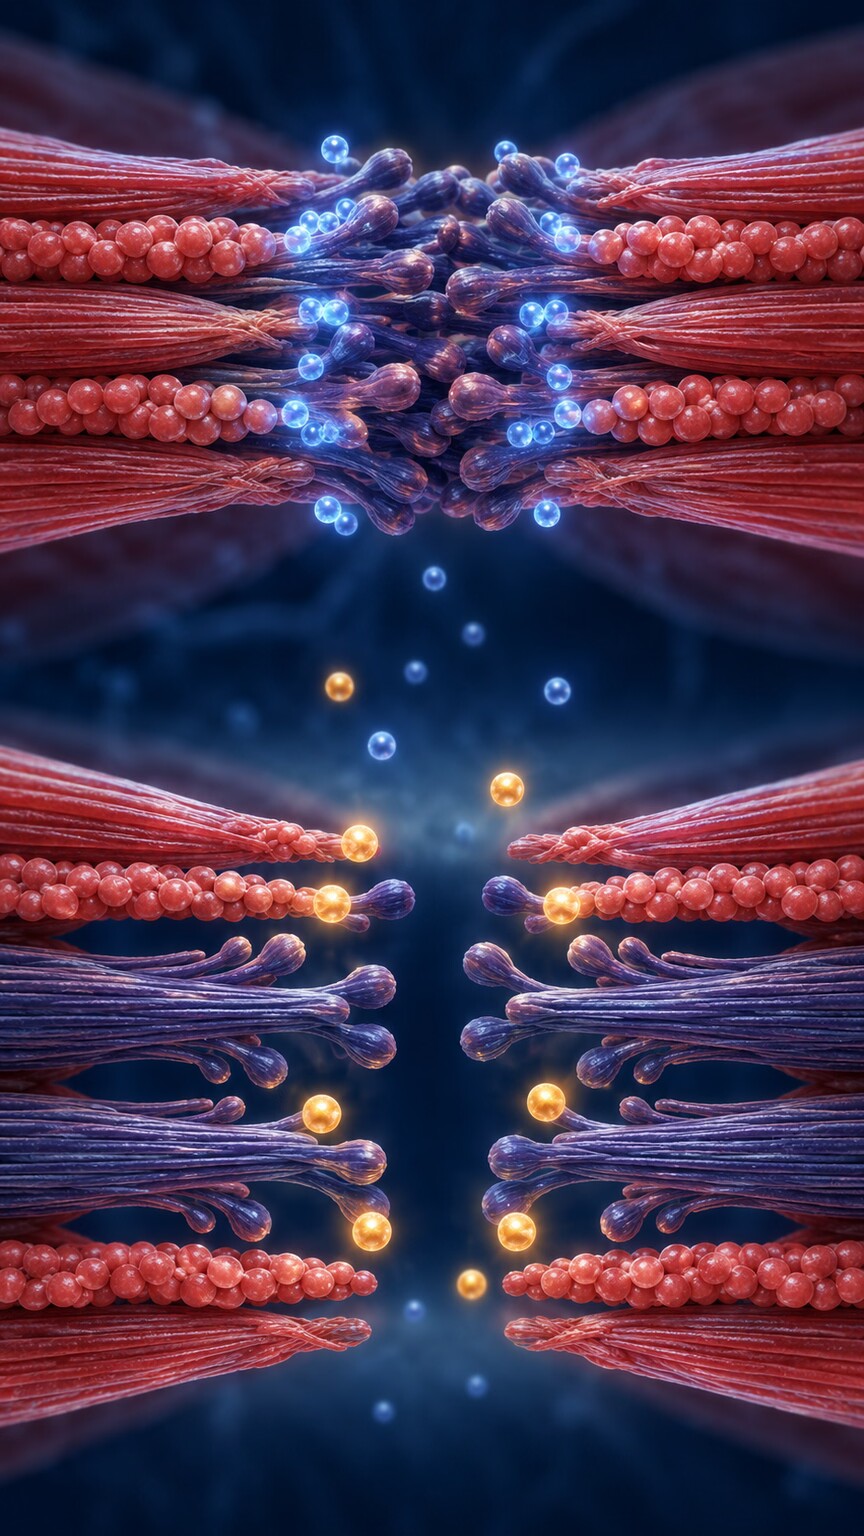
Figure 4. Magnesium physically competes with calcium at the muscle fiber level, and adequate magnesium supports muscle relaxation — a mechanism that helps explain restless legs and nighttime muscle tension in deficiency.
The often-repeated claim that magnesium "relaxes muscles" has a genuine physiological basis worth explaining specifically, since it's frequently mentioned without any real mechanism attached. Muscle contraction depends on calcium entering muscle fibers and triggering the physical sliding action that shortens the muscle; magnesium acts as a natural counterbalance to this process, competing with calcium at the cellular level and supporting the muscle's return to a relaxed state once a contraction signal ends. When magnesium runs low, calcium's contracting effect can go relatively unopposed, contributing to muscle tension, cramping, and the restless, twitchy sensations some people report specifically at night when trying to fall asleep — a physical, muscular contributor to disrupted sleep that operates independently of the brain-level receptor mechanisms described earlier, but frequently shows up in the same deficient individuals at the same time.
This same calcium-magnesium competitive relationship extends specifically to a condition many people experience directly at night: nocturnal leg cramps, the sudden, often painful muscle seizing that can jolt someone awake from otherwise sound sleep. The mechanism described above — calcium driving contraction, magnesium supporting the return to relaxation — plays out at the level of individual muscle fibers in the calf and foot particularly prone to this kind of cramping, and several clinical studies have specifically examined magnesium supplementation as an intervention for nocturnal leg cramps, with mixed but generally favorable results reported in populations with an identifiable magnesium insufficiency to begin with. This gives the often-repeated recommendation to try magnesium for nighttime leg cramps a genuine mechanistic basis, distinct from the sleep-onset and sleep-maintenance mechanisms discussed elsewhere in this article, even though all of these effects can plausibly overlap in the same person experiencing several different symptoms simultaneously.
Restless legs syndrome, a related but clinically distinct condition characterized by an uncomfortable, often hard-to-describe urge to move the legs specifically when at rest, particularly in the evening and at night, has also been studied in relation to magnesium status, though the evidence here is considerably less conclusive than for simple nocturnal cramping. Restless legs syndrome is understood to involve several distinct underlying mechanisms, including a well-established connection to iron metabolism in specific brain regions, meaning magnesium is, at most, one of several possible contributing factors worth investigating rather than a primary, well-established cause on its own. This distinction matters practically: someone experiencing restless legs specifically, as opposed to simple cramping, benefits from a broader evaluation — including iron studies — rather than assuming magnesium alone explains the full clinical picture.
What Magnesium Deficiency-Related Sleep Disruption Actually Looks Like
Given the several distinct mechanisms described above, magnesium-related sleep disruption tends to present with a recognizable combination of features rather than simple difficulty falling asleep alone. Frequent nighttime awakenings, a sense of restlessness or an inability to fully settle even after falling asleep, muscle cramps or restless legs specifically at night, and sleep that feels physically unrefreshing despite adequate hours are the pattern most consistently described in the research connecting magnesium status to sleep quality. This differs somewhat from classic stress- or anxiety-driven insomnia, which more often centers on racing thoughts preventing sleep onset in the first place; magnesium-related disruption more frequently shows up as trouble maintaining sleep once it starts, consistent with the excitability and muscle-tension mechanisms discussed throughout this article operating continuously through the night rather than only at the moment of trying to fall asleep.
This distinction between sleep-onset difficulty and sleep-maintenance difficulty is well recognized in sleep medicine generally, and it's worth understanding why the mechanisms described in this article map more naturally onto the maintenance side of that distinction. Falling asleep initially involves a relatively brief transition window, while staying asleep through a full night requires sustained inhibitory tone and appropriately low excitatory signaling continuously across several hours and multiple sleep cycles. A magnesium-related reduction in the NMDA receptor's blocking effect, or a less effective GABA system, wouldn't necessarily prevent the initial transition into sleep if enough natural sleep pressure has built up over the day — but it could plausibly make it harder to maintain that lowered-excitability state consistently through the night, allowing brief arousals or lighter, less stable sleep stages to intrude more readily than they would with fully adequate magnesium support.
Sleep architecture itself — the specific sequence and proportion of different sleep stages a person cycles through overnight — provides another angle on this same pattern. Deeper, slow-wave sleep stages are associated with particularly pronounced inhibitory brain activity, representing the periods when the calming GABA-driven signaling described earlier is most dominant relative to excitatory glutamate signaling. Some research examining magnesium supplementation has specifically reported increases in the proportion of time spent in these deeper sleep stages, alongside reductions in nighttime awakenings, a pattern consistent with magnesium's proposed mechanisms operating specifically on the maintenance and depth of sleep rather than dramatically altering how quickly someone initially falls asleep.
A Worked Example: Two People, Two Different Sleep Complaints

Figure 5. Difficulty falling asleep and difficulty staying asleep often point toward different underlying mechanisms, which is part of why the specific pattern of a sleep complaint carries diagnostic value.
Consider someone whose main complaint is lying awake for an hour or more with a racing mind before finally falling asleep, but who then sleeps through the night without issue once sleep begins. This pattern points more toward psychological or stress-driven insomnia — the acute racing-thoughts presentation — and while addressing magnesium status is a reasonable general step, the primary intervention more likely involves stress management, sleep hygiene, or addressing an anxiety-related driver directly.
Now consider someone who falls asleep within minutes without difficulty, but wakes up three or four times overnight, sometimes with mild calf cramping, and wakes in the morning feeling physically unrested despite technically sleeping seven or eight hours. This pattern — easy sleep onset paired with fragmented, physically restless maintenance of sleep — aligns much more closely with the mechanisms described throughout this article: reduced NMDA-receptor gating allowing excitability to creep back in partway through the night, muscle-level tension contributing to physical restlessness, and potentially an elevated overnight cortisol pattern. For this second presentation, checking magnesium status directly, alongside a review of diet, alcohol intake, and medications known to lower magnesium, is a considerably more targeted next step than it would be for the first, racing-thoughts presentation.
A third scenario helps illustrate how these mechanisms can layer together rather than appearing in isolation. Consider someone under significant, sustained work stress who also drinks alcohol most evenings to "unwind" — a combination worth examining specifically, since alcohol is independently well documented to increase magnesium excretion through the kidneys, meaning this person is simultaneously experiencing the stress-driven magnesium loss described earlier and a second, additive source of magnesium depletion from alcohol use. Their sleep complaint might combine several features discussed throughout this article at once: some difficulty settling down initially due to residual daytime stress activation, followed by fragmented, restless sleep through the night with occasional cramping, followed by cortisol-driven early-morning waking before they feel adequately rested. Addressing this presentation effectively would reasonably involve looking at the alcohol use and stress load directly, alongside magnesium status, rather than treating any single factor in isolation as the full explanation — a genuine illustration of how these several mechanisms, each individually well-documented, frequently compound each other in real-world presentations rather than appearing as clean, single-cause cases.
Why Blood Magnesium Doesn't Always Reflect What's Happening at the Receptor Level
Figure 6. Only about 1 percent of the body's total magnesium circulates in blood serum, with the remainder stored in bone and inside cells — a distinction that explains why a normal blood test doesn't fully rule out functional deficiency.
A genuinely important complication for anyone trying to connect a blood test result to the sleep mechanisms described throughout this article: less than 1 percent of the body's total magnesium actually circulates in the bloodstream at any given time, with the vast majority stored inside bone and within cells themselves. The body works actively to keep blood magnesium within a narrow, stable range, pulling from these internal stores when intake is temporarily low — which means a standard serum magnesium blood test can return a normal result even when cellular and bone stores are becoming genuinely depleted, since blood levels are often the last thing to actually drop.
This matters directly for interpreting the sleep-related mechanisms in this article, since the NMDA receptor, GABA system, and muscle fibers described earlier are all responding to magnesium availability at the cellular and neuronal level, not to the blood serum number itself. Someone can have a technically normal blood magnesium result while still experiencing a meaningful degree of cellular-level depletion affecting these specific receptor systems, which is part of why some clinicians rely on symptom patterns and risk factors (alcohol use, certain medications, gastrointestinal conditions affecting absorption, chronic stress) alongside blood testing, rather than treating a single normal serum result as fully ruling out a magnesium contribution to a sleep complaint.
Understanding why the body prioritizes keeping blood magnesium so tightly stable, even at the expense of internal stores, adds useful context here. Magnesium is required for a wide range of time-sensitive processes throughout the body, including normal heart rhythm and nerve conduction, both of which depend on blood magnesium staying within a narrow functional range on a moment-to-moment basis. Given how critical these functions are, the body treats maintaining stable blood magnesium as a higher physiological priority than protecting bone and cellular reserves, essentially sacrificing the deeper stores first when intake falls short, precisely so that blood levels — and the immediately life-relevant functions depending on them — remain protected for as long as possible. This priority system is exactly why blood testing alone can be a genuinely late indicator of an underlying magnesium shortfall that's already been affecting cellular-level processes, including the sleep-related mechanisms discussed throughout this article, for some meaningful period of time before blood levels themselves ever show a measurable change.
Several specific circumstances make this hidden, cellular-level depletion considerably more likely, and are worth mentioning specifically since they help identify who might benefit most from looking beyond a single normal blood test. Chronic gastrointestinal conditions affecting nutrient absorption, long-term use of certain medications including some diuretics and proton pump inhibitors, poorly controlled diabetes (which increases urinary magnesium loss), and, as discussed earlier, chronic alcohol use and sustained psychological stress, all represent situations where cellular magnesium depletion can meaningfully outpace what a single blood draw would suggest. Anyone experiencing the specific sleep-maintenance pattern described earlier in this article, particularly alongside one or more of these risk factors, has a reasonable case for discussing magnesium status more thoroughly with a healthcare provider, even if an initial standard blood test happens to come back within the normal range.
More specialized tests, including red blood cell magnesium or a magnesium loading test, exist specifically to get a more accurate picture of these deeper stores when standard serum testing leaves genuine ambiguity.Frequently Asked Questions
Does taking magnesium make you fall asleep faster, like a sedative?
Not typically in the same way a sedative does. Magnesium supports the nervous system's ability to downshift into a calmer state through receptor-level mechanisms, but it doesn't force sleep onset the way prescription sleep medications are designed to.
Can too much magnesium disrupt sleep instead of helping it?
Excessively high magnesium is uncommon from diet or standard supplementation in someone with normal kidney function, and it wouldn't specifically disrupt sleep through the mechanisms described here, though very high doses can cause gastrointestinal discomfort that itself interferes with rest.
Which is more relevant for sleep: magnesium's effect on NMDA receptors or GABA receptors?
Both are considered relevant and are thought to work together rather than one being clearly dominant — the NMDA effect reduces excess excitatory signaling while the GABA effect supports the brain's calming inhibitory signal, a coordinated two-sided mechanism.
Does chronic stress lower magnesium, or does low magnesium cause stress?
Evidence points both directions, creating a potentially self-reinforcing cycle: chronic stress increases magnesium loss through the body, while low magnesium reduces the body's ability to properly regulate its own stress-response system.
Can restless legs at night be a sign of low magnesium?
It can be one contributing factor among several, given magnesium's role in muscle relaxation, though restless legs syndrome has multiple possible causes and isn't attributable to magnesium status alone in every case.
Why did my blood magnesium come back normal even though I have sleep-maintenance issues?
Blood magnesium represents under 1 percent of total body magnesium and is tightly regulated, so it can remain normal even as cellular and bone stores become depleted, since the body draws on those deeper reserves first.
How long does it typically take to notice a sleep improvement from magnesium?
Many people report needing several days to a few weeks of consistent intake before noticing a change, consistent with magnesium's role as a gradual cofactor-support mechanism rather than a fast-acting sedative effect.
Conclusion
Magnesium's connection to sleep quality isn't a single vague effect — it operates through at least four distinct, identifiable pathways: directly gating excitatory signaling at the NMDA receptor, supporting the brain's primary inhibitory GABA system, serving as a cofactor in melatonin production, and helping regulate the cortisol-driven stress-response axis, alongside a separate muscular relaxation effect at the fiber level. Understanding which of these mechanisms is most relevant to a specific sleep complaint — trouble falling asleep versus trouble staying asleep, racing thoughts versus physical restlessness — is what turns "magnesium helps with sleep" from a vague wellness claim into a genuinely useful, mechanism-based piece of information.
It's also worth carrying forward the practical implication of the blood-testing limitation discussed earlier: because standard serum magnesium can look reassuringly normal even during meaningful cellular depletion, the pattern of a sleep complaint — and the presence of known risk factors like chronic stress, alcohol use, or certain medications — often carries more diagnostic weight than a single blood value considered in isolation. Someone recognizing the specific combination described in this article — easy sleep onset paired with fragmented, physically restless overnight sleep, possibly alongside cramping or a demanding, stress-heavy period in their life — has a genuinely reasonable, mechanism-supported case for discussing magnesium status with a healthcare provider, rather than dismissing it simply because a routine blood panel came back within range.
Still Not Sure What Your Results Mean?
Upload your labs and get a complete, visual, plain-language interpretation of every biomarker — delivered to your inbox in under 15 minutes.
Get My ReportThis article is for educational purposes only and does not constitute medical advice. Always consult your healthcare provider regarding your specific lab results.